How Much Can A Nail Fungus Treatment Clinic Owner Make On $436M Revenue
Nail Fungus Treatment Clinic Bundle
A nail fungus treatment clinic owner can make very little in the first year if payroll and ramp-up costs outrun patient volume, then materially more as provider utilization improves In the researched assumptions, Year 1 revenue is $680,640 with a -$83,226 operating loss after payroll, including a $185,000 lead podiatrist salary By Year 2, revenue reaches $1,447,920 and operating profit is $352,780 before taxes, financing, reserves, and owner distributions By Year 5, the model shows $4,362,840 in revenue and $2,729,686 in operating profit, but that is not guaranteed compensation
Owner income$102k-$2.9MNet margin0.3%-61.7%Revenue for target pay$1.45MBusiness difficultyHard
Want to test your owner pay target?
Owner income calculator
Estimate owner take-home and the target-pay gap from monthly revenue, gross margin, payroll, overhead, marketing, reserves, and target pay.
!
Planning note: This is a researched planning estimate only, not guaranteed salary, tax advice, or owner distribution advice. Actual owner income depends on collections, payroll, taxes, debt, and reinvestment needs.
Want the six owner-income drivers?
1
Paid Starts
$681K-$4.36M
More paid treatment starts drive the jump from Year 1 revenue to Year 5, so this is the biggest swing in owner take-home.
2
Case Price
$85-$315
Higher treatment pricing and a better case mix lift cash per visit and raise gross profit fast.
3
Provider Use
45%-85%
Higher provider capacity spreads salary cost across more visits, which improves margin and payback.
4
Margin Mix
26%-19.5%
A lower variable cost load leaves more revenue after supplies, lab fees, and antifungals.
5
Referral Cost
10%-6.5%
Lower marketing and referral spend keeps more of each new patient dollar for the owner.
6
Fixed Overhead
$12.7K/mo
Rent, insurance, and admin costs set the break-even floor, and reserves decide how soon the owner can draw safely.
How do you check owner income in the Nail Fungus Treatment Clinic financial model?
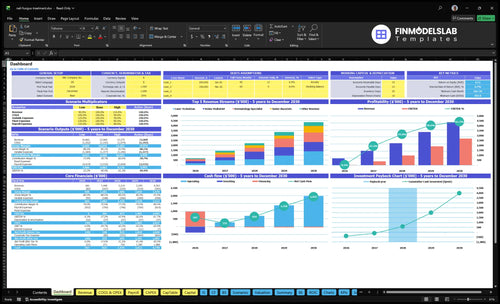
This Nail Fungus Treatment Clinic Financial Model Template lays out a five-year forecast with dashboard, assumptions, income outputs, scenarios, and owner income views; it tracks provider counts, monthly treatments, pricing, COGS, wages, overhead, reserves, and distributions, with revenue rising from $680,640 to $4,362,840, operating profit from -$83,226 to $2,729,686, and margin from -122% to 626%. Open the model.
Owner-income model highlights
Owner take-home is visible
Profit swings sharply up
Scenarios test key assumptions
Can a nail fungus clinic scale beyond the owner?
Yes, the Nail Fungus Treatment Clinic can scale beyond the owner, but only if it keeps provider time full and referral flow steady. In Year 1, the model uses 1 senior podiatrist, 1 dermatology specialist, 1 laser technician, 1 medical assistant, and no junior associate, with revenue at $680,640. By Year 5, staffing grows to 2 senior podiatrists, 2 dermatology specialists, 4 laser technicians, 3 medical assistants, and 2 junior associates, and revenue reaches $4,362,840.
A Nail Fungus Treatment Clinic owner can make $185,000 in salary if the owner is the lead podiatrist, but Year 1 still shows -$83,226 operating profit on $680,640 revenue after payroll, so that salary may need reserves or owner funding; see How To Write A Business Plan For Nail Fungus Treatment Clinic? for the planning steps behind this model. By Year 2, the clinic shows $352,780 operating profit before taxes and reserves, and by Year 5 it reaches $2,729,686 operating profit on $4,362,840 revenue, but salary, profit, and distributions are separate cash streams.
Owner-operator pay
Lead podiatrist salary: $185,000
Year 1 revenue: $680,640
Year 1 operating profit: -$83,226
Year 1 margin: -12.2%
Profit upside
Year 2 operating profit: $352,780
Year 5 revenue: $4,362,840
Year 5 operating profit: $2,729,686
Year 5 operating margin: 62.6%
How many nail fungus patients are needed to pay the owner?
The Nail Fungus Treatment Clinic needs about 359 treatments a month at roughly $184 each to cover the owner-pay base. That equals about $66,100 in monthly revenue, because the 26% variable load leaves about $136 contribution per treatment and fixed payroll plus overhead is about $48,908. The $185,000 lead podiatrist salary is already inside that payroll base, so the real swing factors are conversion, pricing, utilization, staffing, and marketing efficiency.
Break-even math
308 treatments = $56,720 monthly revenue
$184 revenue per treatment
26% variable load
$136 contribution per treatment
What moves the number
359 treatments covers fixed costs
$48,908 monthly payroll plus overhead
$185,000 lead podiatrist salary included
Conversion and utilization drive profit
Key Takeaways
Paid starts drive revenue; consults only matter if booked.
Utilization must rise to cover heavy payroll.
Variable costs stay high, so mix and collections matter.
Fixed overhead and equipment cuts distributable cash.
Owner income scenario comparison for low, base, and high cases
Owner income scenarios
Owner income shifts with treatment volume, staffing, and fixed clinic overhead. The low case stays tight at launch, while higher utilization turns the same clinic into much stronger take-home.
Low, base, and high cases show how volume and staffing change owner income.
Scenario
Low CaseLow Case
Base CaseBase Case
High CaseHigh Case
Launch model
Launch month volume stays thin, so revenue only partly covers labor and overhead.
The clinic runs at the modeled Year 3 level with steadier volume and a more balanced cost base.
The clinic reaches the Year 5 run rate, where higher volume pushes owner income sharply higher.
Typical setup
Year 1 revenue is $680,640, variable costs run at 26%, payroll plus fixed overhead is $586,900, and operating profit is -$83,226.
Year 3 revenue is $2,218,560, variable load is about 22.5%, payroll plus fixed overhead is $761,400, and operating profit is $957,984.
Year 5 revenue is $4,362,840, variable load is about 19.5%, payroll plus fixed overhead is $782,400, and operating profit is $2,729,686.
Cost drivers
Year 1 volume
26% variable cost load
$586,900 payroll and overhead
thin launch utilization
owner salary pressure
Year 3 volume
22.5% variable load
$761,400 payroll and overhead
steadier staffing
stronger capacity use
Year 5 volume
19.5% variable load
$782,400 payroll and overhead
near-full capacity
more add-on treatments
Owner income rangeBefore owner reserves
-$83,226Loss at launch
$957,984Modeled profit
$2,729,686Upside case
Best fit
Use this to test owner take-home if ramp is slow or the clinic starts underfilled.
Use this as the main planning case for hiring, cash flow, and owner draw decisions.
Use this to stress-test owner take-home when capacity is near full and demand stays strong.
!
Planning note: Scenario figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, or distributions.
Nail Fungus Treatment Clinic Core Six Income Drivers
Paid treatment starts
Paid treatment starts
Paid treatment starts are the cash gate for this clinic. Year 1 volume is about 308 completed treatments per month, rising to about 1,770 per month by Year 5. Each added start lifts revenue, then pays for supplies, lab fees, antifungal costs, marketing, and billing fees before owner take-home.
Track qualified consults, consult-to-start conversion, and appointment capacity. If referrals are weak, reviews slip, or patients won’t pay, starts fall fast. More web traffic alone does not help unless it turns into paid starts.
Track start rate, not traffic
Measure starts per qualified consult, not clicks. A useful dashboard shows booked consults, show rate, accepted plans, and open chair time. If consults are solid but starts lag, the issue is usually trust, pricing, or follow-up. If starts are strong but schedules are full, the bottleneck is capacity.
At 308 starts per month, even a small conversion gain matters. By 1,770 starts per month, missed slots become lost revenue you can’t get back. Since every paid start contributes after variable costs, the fastest path to owner pay is better conversion plus enough appointment supply to deliver it.
Track qualified consult-to-start rate.
Watch referrals and reviews.
Match capacity to demand.
Provider utilization
Provider utilization
Provider utilization is the share of paid staff time that turns into billable visits. In this model, senior podiatrist utilization rises from 45% to 85%, dermatology specialist from 40% to 80%, laser technician from 50% to 85%, and medical assistant from 60% to 85%. With payroll heavy, including a $185,000 lead podiatrist and $210,000 staff dermatologist, underfilled schedules cut owner income fast.
Here’s the quick math: more filled rooms and support time spread fixed payroll across more treatments. If schedules stay thin, wages stay fixed while revenue lags, so profit and owner draw get squeezed even when demand exists. The key inputs are booked hours, visit mix, no-shows, and room capacity.
Keep schedules full
Track utilization weekly by role, not just total visits. Measure booked hours divided by available hours, then compare each provider to the 85% target. Separate clinical time from admin time so you can see where capacity is leaking.
Use block scheduling, tighter recall, and faster handoffs from consult to treatment starts. If a provider sits below 40% to 50% for long, the clinic is paying for idle payroll, and owner cash flow drops before revenue can catch up.
Fixed overhead and reserves
Fixed overhead and reserves
$12,700 a month in fixed overhead comes off cash before wages: $6,500 rent, $2,500 malpractice insurance, $800 software, and $1,200 utilities and medical waste. That is $152,400 a year before payroll. Add Year 1 payroll of $434,500 and cash pressure is real, even if bookings look solid.
Owner pay depends on revenue after these fixed costs and a reserve line. Since reserves are not provided, model them as an editable deduction before distributions. Ramp-up equipment also drains cash: two laser systems at $85,000 each means $170,000 that has to be funded without starving operating cash.
Track cash burn before owner pay
Use a simple monthly model: revenue minus variable costs, minus $12,700 fixed overhead, minus payroll, minus reserves. If Year 1 payroll averages $36,200/month and Year 5 payroll reaches $52,500/month, the owner only gets paid from what is left after those layers.
Set a reserve target tied to months of overhead and payroll, then test it each forecast update. If rent, insurance, or staffing rises and reserves stay flat, distributable cash shrinks fast. The clean metric is cash after fixed costs, not revenue alone.
Track monthly overhead by line item.
Separate reserves from profit.
Fund equipment from cash plans.
Revenue per treatment plan
Revenue per treatment plan
Revenue per plan is the cash value of one completed care plan, built from visit prices, diagnostics, and follow-up timing. The model uses a $184 weighted average in Year 1 and $205 in Year 5, so the same volume lifts gross revenue before labor or supply cuts matter. At 200 plans a month, that gap is about $4,200 more monthly revenue, which can move owner pay fast.
Raise plan value, not just volume
Track average revenue per completed plan by provider mix, payer mix, follow-up count, and collection rate. The disclosed price inputs are $250 to $290 for senior podiatrist visits, $275 to $315 for dermatology specialist visits, $150 to $170 for laser technician visits, and $85 to $105 for medical assistant visits. Pricing is a financial assumption, not a treatment recommendation.
Measure cash collected per plan.
Test follow-up frequency by payer.
Watch diagnostics and collection delays.
Higher plan value helps owner income before cost cuts matter, but what this estimate hides is weak payer mix or slow collections. If billed revenue rises while cash lags, the clinic can look busy and still struggle to pay the owner. Cash collected beats billed revenue.
Marketing efficiency and referrals
Referral-Driven Patient Acquisition
This driver is the cost to win each new patient, measured by patient acquisition cost (CAC), plus billing processing fees at 4% of revenue. In Year 1, marketing and referrals are modeled at 10% of revenue; by Year 5, they rise to 65% of revenue. If accepted treatment plans do not grow with spend, owner profit and cash for draws fall fast.
Track treatment starts, consult-to-start conversion, collections, repeat visits, and referral mix. Referrals from podiatry, dermatology, and primary care can cut paid spend, but only if those leads convert and pay. Here’s the quick math: if spend grows faster than starts, each new patient adds less profit, even when top-line revenue looks busy.
Measure Starts, Not Clicks
Set spend by paid treatment starts, not clicks. Hold a simple funnel: leads, consults, accepted plans, paid starts, collections, and repeat visits. If marketing rises faster than starts, pause weak channels and shift budget to the referral sources that close best. The goal is lower acquisition cost per start, not more traffic.
Track cost per paid start monthly.
Split referral and paid channels.
Watch collections by source.
Cap spend when starts stall.
Treatment mix and gross margin
Treatment mix and gross margin
The clinic’s margin changes with the mix of provider visits, laser sessions, lab work, medication, appointment time, and how fast cash is collected. At 12% COGS in Year 1, gross margin is about 88%; at 9% COGS by Year 5, it is about 91% before marketing and billing. That margin is what funds rent, payroll, and owner pay.
Higher-price visits do not always earn more profit. A $250–$315 specialist visit can beat or lose to a lower-price technician visit if it uses more chair time or paid staff time. The model also shows total variable cost load at 26% in Year 1 and 195% in Year 5, so the mix must be checked against collected cash.
Track margin by treatment plan
Track margin by treatment plan, not by booked revenue. For each visit type, capture collected dollars, supply cost, lab cost, medication cost, and minutes in chair. That shows which service mix actually creates gross profit and which one just fills the schedule.
Compare collected margin per hour.
Cut low-margin follow-up time.
Watch denials and slow collections.
Test staffing against visit mix.
If a service looks good clinically but burns payroll, separate the clinical win from the financial win. The owner gets paid from cash margin, so a slow collection pattern or a long appointment can shrink take-home even when pricing is strong.
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Choosing a selection results in a full page refresh.