How Do Revenue and Margin Affect Owner Pay in a Peptide Therapy Clinic?
Peptide Therapy Clinic Bundle
A U.S. owner-operated Peptide Therapy Clinic can reasonably model about $186,000 a year of owner income in a stabilized base case, with a practical planning range of roughly $68,000 to $328,000 across conservative and stronger-demand scenarios. The base case assumes about $110,000 of monthly revenue, a 58% gross margin after medications, lab-related direct costs, supplies, and payment processing, then $40,000 a month of non-owner payroll, fixed overhead, marketing, and debt service. The $186,000 figure is residual owner cash after a modeled 25% tax reserve and 10% reinvestment reserve; it is not guaranteed salary, does not promise that every peptide can legally be prescribed or compounded, and does not replace entity-specific tax, medical, pharmacy, or legal advice.
Owner income$186KNet margin14%Revenue for target pay$1.21MBusiness difficultyHard
How much can a Peptide Therapy Clinic owner realistically make?
For this article, the clinic is a physician-led, cash-pay practice that evaluates patients, orders or reviews labs when clinically appropriate, prescribes eligible therapies, coordinates dispensing through compliant pharmacies, and follows patients over time. Public U.S. clinic prices show why revenue can scale quickly without thousands of monthly visits: one Charlotte practice lists peptide therapy starting at $299, while a Louisiana clinic publishes $299 and $399 monthly tiers. Those are market examples, not endorsements of any drug, indication, safety claim, or compounding pathway.
The base model uses a $375 realized monthly revenue per active patient-equivalent. At $110,000 monthly revenue, that is about 293 active patient-months. “Active patient-equivalent” is more useful than visits because a recurring program may include medication, shipping, monitoring, and periodic clinical follow-up rather than one billable office visit every month. The owner’s economic job is to convert that recurring patient base into gross profit without treating medication spend, lab expense, acquisition cost, or their own clinical labor as free.
Revenue is the top line; gross profit remains after non-labor direct therapy costs. Operating profit then subtracts non-owner labor and overhead, but it still is not a safe distribution. Owner salary pays for work performed; distributions come from residual profit. Safe owner cash comes only after debt service, taxes, compliance, working capital, and reinvestment are funded. The calculator therefore keeps owner pay below operating costs instead of hiding it inside payroll.
Owner income calculator
Estimate owner take-home from patient revenue, direct-cost margin, staffing, overhead, financing, and reserves.
i
Planning note: Research-based planning estimate only. It is not guaranteed salary, tax advice, medical advice, or owner distribution advice.
1
Active patient volume and retention
293 patient-months
The base case needs about 293 active patient-equivalents at $375 realized monthly revenue. Replacing churn with paid acquisition consumes cash before owner draws.
2
Realized program price
$375/month
The price sits between $299 and $399 market examples; a $25 shift across 293 patients changes monthly revenue by about $7,325.
3
Direct therapy cost and gross margin
58% base margin
Medication, labs, supplies, shipping, and merchant cost sit before payroll; a five-point margin miss removes $5,500 of monthly gross profit.
4
Owner clinical role and staffing
$16K non-owner payroll
The base is owner-operated; a full employed physician replacement can add roughly $20,000 a month of base salary equivalent before payroll burden.
5
Acquisition efficiency
$9K/month marketing
Tie acquisition spending to retained gross profit; the planning target is blended CAC below about $300 with multi-month retention.
6
Compliant treatment menu
0% tolerance for invalid revenue
Remove any revenue line that depends on a peptide, claim, pharmacy pathway, or prescribing practice the clinic cannot support compliantly.
Want to test patient volume, margin, and owner pay in a full forecast?
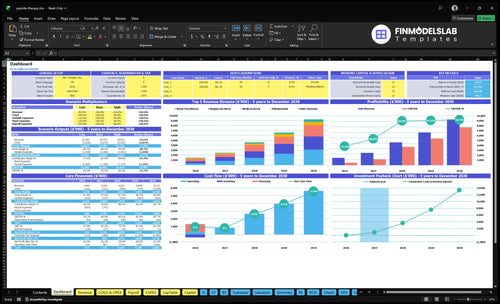
The dashboard preview helps connect active patient assumptions, service mix, revenue, gross margin, payroll, cash flow, and scenario outputs. That is useful for testing whether owner income survives a slower ramp, higher pharmacy cost, another hire, or a larger compliance budget.
What revenue level supports a $144,000 owner income target?
At the base 58% gross margin and $40,000 monthly operating-cost load, the calculator requires about $100,796 a month, or $1.21 million a year, to support a $12,000 monthly owner-pay target after the 25% tax reserve and 10% reinvestment reserve. At the modeled $375 realized monthly revenue per active patient-equivalent, that is about 269 active patient-months. At a published $299 price point it would take about 337; at $399 it would take about 253, which is why the market examples on the published clinic pricing page matter to capacity planning.
Operating break-even first
Base operating costs are $40,000 a month before owner pay and reserves.
At a 58% gross margin, operating break-even is about $68,966 of monthly revenue.
That is only the point where the clinic covers modeled operating costs; it does not fund owner take-home.
The target-pay formula raises the required monthly revenue to about $100,796.
Capacity test
269 active patient-equivalents at $375 support the base target-pay revenue.
A 10% price discount without lower direct cost increases the required patient count.
A 10% retention improvement can be worth more than 10% more leads because it avoids replacement acquisition cost.
Track active patients, realized revenue per active patient, and cancellations together.
Can the clinic run without the owner seeing patients?
It can, but the economics change sharply because this base case assumes the owner supplies clinical leadership and a meaningful share of patient care. The Bureau of Labor Statistics reports a May 2024 physician-and-surgeon median wage at or above $239,200 a year. That is roughly $19,900 a month before payroll taxes, benefits, recruiting cost, and any premium for a hard-to-fill role. Adding even $20,000 of monthly physician payroll to the base model would reduce modeled owner income from $185,640 to roughly $29,640 a year after the same reserves unless revenue or margin also rises.
Owner salary and distributions still need separate tax treatment even though the calculator shows one residual owner-income number. For an S corporation, IRS reasonable-compensation guidance generally requires shareholder-employees to receive reasonable compensation for services before non-wage distributions. The clinic must therefore fund the owner’s labor value before calling the remainder investment profit.
Owner-operated base case
The owner functions as clinician and medical leader.
Non-owner payroll is modeled at $16,000 a month.
Residual owner cash compensates both labor and ownership risk.
Entity-specific payroll versus distribution treatment is handled outside this operating model.
Manager-run or investor-owned case
Add the full replacement cost of licensed clinical coverage.
Do not call owner absence “passive income” until that payroll is funded.
Raise patient capacity only if the additional provider actually has demand.
Distributions should come after replacement labor, debt, taxes, and reserves.
What margin leaves cash after medication, labs, and payroll?
The base case uses a 58% gross margin, meaning 42 cents of each revenue dollar is reserved for medication acquisition, lab-related direct expense, supplies, shipping, and payment processing before payroll. This is a planning assumption rather than a published peptide-clinic benchmark because pharmacy pricing, formulations, patient-specific prescriptions, lab panels, shipping, and payer arrangements vary too widely to defend one national COGS percentage. Labor is then modeled separately so it is not deducted twice.
BLS reports May 2024 median annual wages of $93,600 for registered nurses and $44,200 for medical assistants. The $16,000 monthly base payroll therefore assumes a lean owner-clinician model with hired support and payroll burden, not a multi-physician practice. If local wages or staffing needs are higher, raise labor before increasing owner draws.
Base monthly waterfall
$110,000 revenue produces $63,800 of gross profit at 58%.
Non-owner labor, overhead, marketing, and debt total $40,000.
Profit before reserves is $23,800.
Modeled tax and reinvestment reserves total $8,330, leaving $15,470 for the owner.
Margin sensitivity
A one-point gross-margin change at $110,000 revenue moves gross profit by $1,100 a month.
A five-point miss removes $5,500 monthly before reserves.
That can cut annual owner income by more than $40,000 after the modeled reserve percentages.
Track direct pharmacy, lab, shipping, supply, and card cost per active patient.
How do FDA and advertising rules change the income model?
They can change it more than rent. A clinic should never forecast all commercially promoted peptides as interchangeable revenue units. FDA’s current bulk-substance safety-risk page identifies multiple peptide-related substances in Category 2 or in the withdrawn-nomination section and describes safety concerns for compounds such as GHRP-2, GHRP-6, ipamorelin, BPC-157, CJC-1295, and others. FDA’s human drug compounding policies also show that 503A and 503B compounding depends on specific statutory conditions and evolving policy, not a generic “compounded means allowed” rule.
The FTC Health Products Compliance Guidance says health advertising must be truthful, not misleading, and adequately substantiated. Budget legal review and do not base demand on unsupported outcome claims. If a therapy or claim must be removed, fixed labor, rent, software, and debt remain, so the owner-income hit can exceed the lost sales percentage.
Revenue you can underwrite
Services that fit the clinic’s actual state scope and licensure.
Prescriptions and dispensing pathways reviewed for the specific drug and patient.
Claims supported by the evidence standard applicable to health advertising.
Patient demand that survives conservative, compliant messaging.
Revenue to exclude
Any therapy line your counsel or pharmacy cannot support under current rules.
Sales assumptions that depend on unsupported efficacy or safety claims.
Revenue that requires shipping, prescribing, or telehealth coverage outside the clinic’s compliant footprint.
“Best case” sales from products that could not survive a regulatory review.
Key Takeaways
The base owner-operated case produces about $185,640 of annual owner income after modeled tax and reinvestment reserves on $1.32 million of annual revenue.
About $1.21 million of annual revenue is required to support a $144,000 annual owner-pay target under the base margin and cost structure.
Owner clinical labor is a major hidden asset; replacing it with an employed physician can absorb most of the base-case distribution.
Patient retention, direct therapy margin, and a compliant treatment menu matter more than gross lead volume or headline revenue alone.
What do low, base, and high owner-income scenarios look like?
The cases below are coordinated presets, not one-variable sensitivities. The high case adds labor, overhead, marketing, debt service, and reserves as volume grows; the low case keeps minimum fixed costs. The $4,000 monthly base debt payment is a planning allowance, not a quote. For founders using borrowed capital, the SBA 7(a) program can support uses such as working capital, equipment, fixtures, and some startup needs, but actual pricing and maturity depend on the lender and loan purpose.
Owner income scenarios
Three internally consistent operating cases using the same calculator logic for revenue, margin, staffing, overhead, marketing, debt, and reserves.
Peptide Therapy Clinic low, base, and high owner-income planning cases
Scenario factor
Low CaseLow
Base CaseBase
High CaseHigh
Launch modelMonthly revenue and margin
$75,000 monthly revenue
52% gross margin
$110,000 monthly revenue
58% gross margin
$165,000 monthly revenue
62% gross margin
Typical setupOwner role and patient scale
Owner clinician
About 225–230 active patient-equivalents
Lean support team
Owner clinician
About 293 active patient-equivalents
RN, MA and admin coverage
Owner clinician plus expanded provider support
About 385–390 active patient-equivalents
More scheduling capacity
Cost driversMonthly operating cash load
$12,000 labor + $8,500 overhead
$6,500 marketing + $3,000 debt
25% tax and 12% reinvestment reserves
$16,000 labor + $11,000 overhead
$9,000 marketing + $4,000 debt
25% tax and 10% reinvestment reserves
$23,000 labor + $15,000 overhead
$14,000 marketing + $5,500 debt
27% tax and 12% reinvestment reserves
Owner income rangeAfter modeled tax + reinvestment reserves
$68,040/year
$185,640/year
$327,936/year
Best fitOperating interpretation
Early ramp or weaker retention
Price pressure or narrower compliant menu
Stabilized owner-operated clinic
Disciplined direct costs and repeat patients
Strong retained demand
Higher staffing, marketing, overhead, and compliance capacity
i
Planning note: Scenario figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, medical advice, or distribution forecasts.
Which six drivers determine Peptide Therapy Clinic owner income?
The six levers below explain most of the difference between the $68,040 low case and the $327,936 high case. Review them together: volume without retention inflates acquisition cost, price changes can alter conversion, and revenue without clinical capacity creates risk. The AMA Physician Practice Benchmark Survey also shows that practice economics reflect ownership, payment methods, resource cost, and regulatory burden—not demand alone.
1. Active patient volume and retention
Build revenue from retained patient-months, not lead volume
The base case needs about 293 active patient-equivalents because $110,000 divided by the $375 realized monthly revenue assumption equals roughly 293. If monthly churn is 8%, about 23 patients must be replaced every month just to stay flat. With a $9,000 marketing budget, paying to replace all 23 would imply about $391 of marketing spend per replacement before considering organic referrals. Retention therefore changes owner cash even when revenue looks stable.
Improving monthly churn from 8% to 6% saves roughly six replacement patients at a 293-patient base. At a $300 blended acquisition cost, that frees about $1,800 a month for growth or cash reserves. Do not distribute it automatically if medication orders, refunds, or compliance work still need funding.
Track the patient base as a cohort
Use patient-month economics so revenue, direct cost, and marketing all reconcile to the same unit.
Active patients at month-end
New starts and cancellations
30-, 90-, and 180-day retention
Revenue and gross profit per active patient
2. Realized program price
Measure realized revenue, not the advertised tier
Published U.S. examples support a planning band around the model’s $375 realized price: one practice lists peptide therapy starting at $299, while another lists $299 and $399 tiers. Discounts, bundled labs, multi-month packages, credits, refunds, and mix can change realized revenue, so forecast cash revenue per active patient rather than the highest menu price.
A $25 realized-price increase across 293 active patients adds about $7,325 of monthly sales and about $4,249 of gross profit at a 58% margin before added overhead. Count the full lift only if churn and the direct cost of the package do not rise materially.
Separate price from mix
Track what patients actually pay and what the package costs to fulfill.
Gross and net revenue per patient
Discount and refund rate
Price by therapy or service line
Conversion rate after price changes
3. Direct therapy cost and gross margin
Protect margin before adding more patients
The base gross-margin assumption is 58%, the low case is 52%, and the high case is 62%. These are planning ranges, not published peptide-clinic benchmarks; they include pharmacy, lab, supply, shipping, and merchant costs but exclude payroll. If the clinic mixes these items with labor, the calculator will overstate or double-count costs.
At $110,000 monthly revenue, each margin point is worth $1,100 of gross profit. Moving from 58% to 53% removes $5,500 a month; after the base reserves, owner cash falls by roughly $3,575 a month, or about $42,900 a year. Track pharmacy and lab cost per patient weekly.
Reconcile the direct-cost ledger
Gross margin should be explainable from invoices and patient-level fulfillment data.
Medication acquisition cost per active patient
Lab and supply cost per protocol
Shipping and payment-processing cost
Gross margin by service line
4. Owner clinical role and staffing leverage
Price the owner’s labor before calling profit passive
The base case carries $16,000 a month of non-owner payroll because the owner is still a working clinician and medical leader. National medians were $93,600 for registered nurses and $44,200 for medical assistants in May 2024; high-cost markets and payroll burden can push actual cost higher.
Removing the owner from patient care without replacement payroll overstates profit. BLS reports physician median wages at or above $239,200 a year before employer burden, nearly $20,000 a month of base wage equivalence. Add a provider only when the capacity and retained gross profit cover the fully loaded cost.
Track labor by productive capacity
Headcount alone does not show whether the payroll creates patient capacity or merely adds fixed cost.
Clinical labor cost per active patient
Provider schedule utilization
Owner clinical hours versus administrative hours
Revenue and gross profit per clinical FTE
5. Acquisition efficiency
Buy retained gross profit, not appointments
The base marketing budget is $9,000 a month, rising to $14,000 in the high case. The increase prevents the high case from assuming revenue growth with flat acquisition spending. The planning target used here is a blended CAC below about $300, paired with at least six months of retention. At $375 monthly revenue and 58% gross margin, six patient-months generate about $1,305 of gross profit before labor and overhead, giving room for acquisition cost without consuming all contribution.
If CAC rises from $300 to $500, 30 new starts consume another $6,000 a month before payroll and fixed cost. Compare channels on retained 90- or 180-day gross profit, not cost per lead; cheap leads can still produce weak owner cash.
Use cohort CAC payback
Channel decisions should be based on the cash contribution from patients who remain active.
Blended and channel-level CAC
Lead-to-consult and consult-to-start conversion
90- and 180-day gross-profit retention
Referral share of new starts
6. Compliant treatment menu
Treat regulatory eligibility as a revenue gate
For peptide therapy, compliance is not a generic overhead percentage. FDA’s current safety-risk materials identify a number of peptide-related bulk substances with significant safety concerns or limited safety information, and its compounding policy distinguishes the conditions that apply under sections 503A and 503B. Validate each therapy, pharmacy source, prescribing pathway, state rule, and patient-specific use instead of assuming the full menu persists.
Run a concentration test. If one therapy line is 20% of $110,000 monthly revenue and disappears while operating costs remain $40,000, revenue falls to $88,000. At 58% gross margin, owner income after the base reserves drops to about $7,176 a month—more than a 50% cut without closing the clinic.
Review revenue concentration quarterly
The clinic should be able to remove one therapy line without creating a cash crisis.
Revenue share by therapy and pharmacy pathway
State licensure and telehealth footprint
Current FDA compounding and safety status
Marketing-claim review and documentation
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Choosing a selection results in a full page refresh.