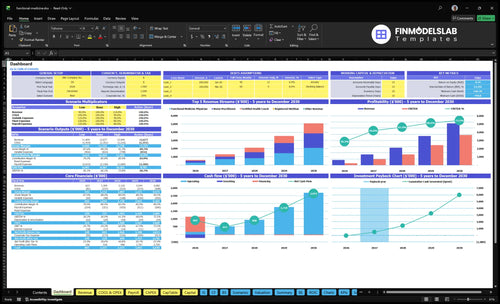
How Much Does a Functional Medicine Practice Owner Make: $238K-$37M
Functional Medicine Practice Bundle
A functional medicine practice owner can make roughly $238K in Year 1 to $3684M in Year 5 in pre-tax owner income capacity, based on the researched model assumptions That range tracks annual collections of $623K to $5082M and EBITDA margins rising from 382% to 725% These are planning assumptions, not guaranteed earnings or tax advice Actual take-home depends on visit volume, pricing, provider utilization, payroll, lab and supplement costs, marketing, reserves, and whether the owner is still doing clinical work
Owner income$238K to $3.7MNet margin38.2% to 72.5%Revenue for target pay$623K to $5.1MBusiness difficultyMedium
Want the six income drivers?
1
Patient Utilization
50%-85%
More filled schedules lift revenue with little extra cost, so take-home improves as provider use rises from 50% to 85%.
2
Visit Price
$150-$510
Higher visit prices raise cash per patient, and the model runs from $150 to $510 per treatment.
3
Recurring Care
$623K-$5.1M
Repeat visits and memberships turn retention into the model's $623K to $5.1M revenue path.
4
Payroll Load
$220K-$450K
Clinician and support hiring expands capacity, but payroll can climb from about $220K to $450K a year.
5
Lab Margin
13% to 10%
Lab kits and supplements fall from 13% of revenue to 10%, so each point saved drops straight to EBITDA.
6
Reserve Buffer
$745K
Clinic overhead runs $17.6K a month, and the $745K cash floor plus debt service can reduce distributions.
Want to calculate owner take-home?
Owner income calculator
Estimate owner take-home and the target-pay gap from revenue, margin, costs, reserves, and target pay.
!
Planning note: Research-based planning estimate only. It is not guaranteed salary, tax advice, or owner distribution advice.
Can a functional medicine practice owner make more by hiring providers?
Yes—hiring can raise revenue capacity in a Functional Medicine Practice, but only if schedule utilization stays high. The model scales from 1 physician, 1 nurse practitioner, and 1 health coach in Year 1 to 4 physicians, 4 nurse practitioners, and 5 health coaches by Year 5, with revenue rising from $623K to $5,082M and EBITDA from $238K to $3,684M. But more providers also add coordination work, support staff, onboarding risk, and payroll pressure, so owner-as-clinician income is not the same as owner-as-operator profit.
Where hiring helps
Fill calendars before adding headcount.
Use utilization to drive growth.
Scale only when demand is steady.
More providers can raise capacity fast.
What can go wrong
Weak utilization turns hires into drag.
Payroll adds fixed cost pressure.
Onboarding can slow cash flow.
Support staff needs rise with providers.
What expenses reduce functional medicine practice owner income?
If you’re asking what cuts owner pay in a Functional Medicine Practice, start with the operating costs: How Much To Launch Functional Medicine Practice? shows the big buckets are direct costs, variable costs, fixed overhead, and payroll. Here’s the quick math: lab test wholesale kits run 8% of revenue in Year 1 and fall to 6% by Year 5, while supplement inventory moves from 5% to 4%.
Direct costs
Lab kits: 8% to 6%
Supplements: 5% to 4%
These hit revenue first
Less volume, less owner cash
Overhead and payroll
Marketing and SEO: 6% to 4%
Medical supplies: 2%
Fixed overhead: $17,550/month
Payroll roles total $220K/year
Is a cash-pay functional medicine practice profitable?
Yes—a cash-pay Functional Medicine Practice can be profitable if pricing and utilization stay on target. Using Year 1 rates of $450 per physician treatment, $325 per nurse practitioner treatment, and $150 per health coach treatment, at 65%, 60%, and 50% utilization, the model produces about $623K revenue and $238K EBITDA. Memberships can help smooth cash flow, but no membership revenue is supplied in the source data.
Year 1 math
$450 physician treatment rate
$325 nurse practitioner rate
$150 health coach rate
$623K revenue at stated utilization
Profit drivers
$238K EBITDA in Year 1
Retention keeps visits full
Compliance supports repeat care
Capacity and delivery cost decide margin
Key Takeaways
Filled clinical hours drive revenue faster than cost cuts.
Small price gains compound across thousands of visits.
Payroll can scale margins or erase owner take-home.
Reserves protect cash before growth turns into profit.
Compare lean, base, and high-growth owner-income scenarios
Owner income scenarios
Owner income rises with provider count, utilization, pricing, and cost control. Early years carry more fixed overhead per visit, while later years spread rent and staff across more volume.
Low, base, and high cases show how staffing and utilization change owner income.
Scenario
Low CaseLaunch
Base CaseScaling
High CaseMature
Launch model
This is the lean launch case with lower owner income in the first operating year.
This is the modeled mid-case with stronger owner income after demand is proven.
This is the stronger earnings path with the highest modeled owner income.
Typical setup
Year 1 shows $623K revenue, $238K EBITDA, 38.2% margin, 1 physician, 1 nurse practitioner, 1 health coach, and 50% to 65% utilization.
Year 3 shows $2.12M revenue, $1.303M EBITDA, 61.5% margin, 2 physicians, 2 nurse practitioners, 3 health coaches, and 75% to 80% utilization.
Year 5 shows $5.082M revenue, $3.684M EBITDA, 72.5% margin, 4 physicians, 4 nurse practitioners, 5 health coaches, and 85% utilization.
Cost drivers
Single-provider volume
early utilization
fixed clinic overhead
launch marketing spend
small care team
Multi-provider volume
higher utilization
better price mix
lower unit costs
steadier overhead absorption
Near-full utilization
larger provider bench
higher visit volume
better fixed cost absorption
premium pricing mix
Owner income rangeBefore owner reserves
$238KLaunch case
$1.3MProven demand
$3.7MScale case
Best fit
Use this to stress-test opening month demand and how fast visits fill.
Use this as the core planning case for a clinic with repeat patient flow and a stable team.
Use this to test what multi-provider scale could produce once the practice is mature.
!
Planning note: These figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, or distributions; reserves, debt service, taxes, and owner salary policy can lower take-home cash.
Functional Medicine Practice Core Six Income Drivers
Patient Volume and Provider Utilization
Booked Visits and Provider Utilization
Booked visits are the top-line engine here. In Year 1, the model uses 80 monthly physician treatments at 65% utilization, 100 nurse practitioner treatments at 60%, and 120 health coach treatments at 50%. By Year 5, that grows to 100, 120, and 140 monthly treatments at 85% utilization, so more of the clinic’s hours turn into collected revenue.
Utilization means the share of available clinical time that gets booked and completed. That matters because fixed overhead is already sitting at $17,550 per month. So when fill rate rises, revenue can grow faster than costs, which lifts profit and owner take-home. The main leak is empty capacity from no-shows, slow onboarding, weak referral flow, and too many open clinical hours.
Fill Open Clinical Hours
Track booked visits, completed visits, and no-show rate by provider each month. Also track open hours by role, because a slot that stays empty is lost revenue you never get back. Here’s the quick math: if utilization moves from 50% to 85%, the same staff time produces much more collected revenue without a matching jump in fixed cost.
Manage this with a tight referral pipeline, fast new-patient onboarding, and reminder systems that reduce missed visits. Tie staffing to demand, not hope. If the clinic adds hours faster than bookings rise, margin gets diluted. If booking quality holds while capacity fills, the owner gets more profit from the same overhead base.
Lab and Supplement Margin
Lab and Supplement Margin
Lab kits and supplements add revenue, but they are not pure profit. In Year 1, lab wholesale kits cost 8% of revenue and supplement inventory costs 5%, so gross margin after these direct costs is about 87%. By Year 5, those costs fall to 6% and 4%, lifting gross margin to 90%.
The owner only keeps what is left after refunds, waste, compliance work, and any pass-through pricing. So $100 of ancillary sales is not $100 of owner income. The key question is whether the product mix is truly needed and turns fast enough to protect cash.
Track SKU Margin, Not Just Sales
Measure each item by revenue, direct cost, refund rate, and expired inventory. If a supplement or kit has weak patient need, it can turn a high-margin sale into dead stock fast. Reorder from actual use, not gut feel.
Price by item margin
Limit pass-through discounts
Document patient need
Count inventory monthly
What this estimate hides: compliance issues and waste can quietly eat the 87% to 90% gross margin range. Tight controls add contribution, but gross sales should still be treated as business revenue, not owner pay.
Average Revenue per Patient
Average Revenue per Patient
If visits are full but cash is still tight, average revenue per active patient is the fastest revenue lever. It moves when physician pricing rises from $450 to $510, nurse practitioner pricing from $325 to $365, and health coach pricing from $150 to $170. Those gains hit every visit, so they can lift collections before you add more staff.
Here’s the quick math: this metric depends on visit mix, care plan attach rate, testing review visits, and follow-up cadence. If the scope is unclear or local demand is price-sensitive, consult-to-care conversion drops, and the higher rate never turns into cash. That cuts gross margin and owner pay.
How to Raise It
Track revenue by provider type, not just total visits. Separate new consults, ongoing care plans, and follow-ups, then compare monthly conversion from consult to ongoing care. If patients see clear value, price rises hold better; if not, the clinic loses bookings.
Measure revenue per active patient monthly.
Test price by provider type.
Watch consult-to-care conversion.
Track follow-up and plan attach rates.
Use price changes only after the service scope is clear in writing. A $60 lift on physician visits, $40 on nurse practitioner visits, and $20 on coach visits compounds across thousands of annual visits, but only if demand holds and the team can explain the value fast.
Fixed Overhead, Marketing, and Reserves
Fixed Overhead and Reserves
Fixed Overhead and Reserves set the ceiling on safe owner pay. Monthly fixed overhead is $17,550, driven by $12,000 rent, $2,500 liability insurance, and $1,200 software, so that cost lands before the owner sees profit. Marketing adds 6% of Year 1 revenue, then falls to 4% by Year 5.
Here’s the quick math: if collections dip, those costs still hit cash. With $235K of upfront capex and a $745K minimum cash need in Month 2, reserves protect payroll and slow months, and they keep owner distributions from draining the clinic too early.
Protect Cash, Then Pay Yourself
Use a monthly cash test: revenue minus $17,550 fixed overhead, minus marketing at 6% in Year 1. Set owner draws only after that math still leaves cash above the $745K Month 2 floor. That keeps pay tied to real collections, not booked visits.
Track overhead as revenue moves.
Track marketing from 6% to 4%.
Hold cash above $745K.
Pause draws in weak months.
Clinician and Support Payroll
Clinician and Support Payroll
Payroll can build scale or wipe out owner pay. This clinic model grows from 1 to 4 physicians, 1 to 4 nurse practitioners, and 1 to 5 health coaches, plus support staff. Support payroll includes a $85K practice manager, $50K patient coordinators, $45K medical assistants, and $40K receptionists, so every added full-time equivalent (FTE) has to earn its keep.
Owner clinical hours are not the same as business profit. If the owner is still seeing patients, that can hide weak delegation or low utilization. The risk is hiring ahead of demand, which raises cash burn before visits fill. The payoff is simple: when provider time is booked and support is tight, payroll turns into capacity; when it isn’t, it cuts directly into take-home income.
Track FTEs Against Filled Visits
Measure visits per paid provider hour, revenue per clinician FTE, and support staff load before adding headcount. Payroll should rise only when booked visits and delegated tasks justify it. One clean rule: if a new hire does not increase filled capacity, it probably lowers owner cash.
Separate owner clinic time from profit.
Test staffing before hiring full-time.
Watch utilization, no-shows, delegation.
Use the mix deliberately: more physicians and nurse practitioners lift capacity, while health coaches and support staff protect delivery. But if low utilization leaves open hours on the calendar, the added $85K, $50K, $45K, and $40K roles can erase margin fast.
Recurring Care and Membership Revenue
Recurring Care Revenue
Recurring care includes memberships, structured follow-up visits, and ongoing access after the first consult. In this model, no membership dollars are included, so adding a recurring plan would raise revenue without relying as much on new-patient volume. The main inputs are active members, retention rate, churn, and delivery cost per follow-up.
One clean rule: if the follow-up plan is valuable and compliant, recurring revenue makes owner income steadier. If access is underpriced or cancellations climb, it can add work faster than cash, and that can squeeze take-home pay.
Improve Retention and Follow-Up Cadence
Track renewal rate, monthly churn, and net revenue per active patient. With fixed overhead at $17,550 per month, recurring care can help cover the base cost even when new consult demand dips. Set a clear follow-up cadence, define what each plan includes, and keep the scope tight so renewals do not create hidden labor.
Test pricing against real support time, not just patient interest. Watch cancellation rates, refund requests, and billing rules closely. The goal is simple: stable cash in, controlled delivery cost out.
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Choosing a selection results in a full page refresh.