What Is the Earning Potential for Medical Supply Store Owners?
Modeled here as an owner-operated U.S. community retailer of home-use medical supplies and durable medical equipment, a Medical Supply Store at about $150,000 in monthly sales, or $1.8M a year, can produce about $192,000 of annual owner income after a 24% tax reserve and 12% reinvestment reserve. A reasonable stabilized planning band is roughly $150,000-$220,000, while this article's low and high presets produce $29,400 and $405,360. The base case uses a 55% product gross margin, $32,000 monthly employee payroll, $16,500 fixed overhead, $5,000 marketing, and $4,000 debt service. It excludes owner salary from payroll, final personal tax liability, guaranteed distributions, and extraordinary capital spending.
Owner income$192KNet margin11%Revenue for target pay$1.68MBusiness difficultyHard
What does a $1.8M medical supply store actually leave the owner?
In the base model, $1.8M of annual revenue becomes $990,000 of gross profit. After employee payroll, fixed overhead, marketing, and $48,000 of annual debt service, profit before reserves is $300,000. Setting aside $72,000 for taxes and $36,000 for reinvestment leaves $192,000 for the owner. The scope is a community retailer of home-use medical supplies and durable medical equipment, consistent with Census NAICS 456199, which includes wheelchair, convalescent-supply, and sick-room-supply retailers.
The 55% gross-margin assumption is separated from payroll because the calculator treats employee labor independently. As an adjacent scale check, AdaptHealth reported 2025 product-and-supply cost at 39.9% of revenue and labor at 23.1%; its scale, payer mix, equipment depreciation, and delivery network differ materially from an independent store. The AdaptHealth 2025 filing supports the line-item separation, not the store's exact margin.
Follow the profit bridge
Revenue: all store, e-commerce, refill, rental, and B2B sales before costs.
Gross profit: revenue after product, inbound freight, payment processing, and other non-labor direct costs.
Operating cash proxy: gross profit minus employee payroll, fixed overhead, and marketing; this article does not claim that figure is GAAP EBITDA.
Salary is not the same as distribution
The calculator excludes owner pay from employee labor, so its $192,000 is the total residual owner-income pool.
A working owner can economically treat part of that pool as pay for management labor and the balance as return on ownership; legal payroll treatment depends on entity and tax facts.
An absentee owner should add a replacement manager to labor before calling the remainder passive income.
Owner income calculator
Test how sales, merchandise margin, payroll, overhead, financing, and reserves change owner take-home.
!
Planning note: Research-based planning estimate only. It is not guaranteed salary, tax advice, or owner distribution advice.
1
Product mix and gross margin
5 pts = $90K/yr
At $1.8M of sales, a five-point change in product gross margin moves annual gross profit by $90,000 before payroll and reserves.
2
Orders, ticket, and repeat sales
+$10K/mo sales
At the base 55% margin, another $10,000 of monthly sales creates $5,500 of gross profit before the labor and fulfillment needed to support it.
3
Inventory cash cycle
15 days = $33.8K
With $67,500 of monthly product cost, cutting average inventory by 15 days can free roughly $33,750 of working capital without changing reported profit.
4
Labor and owner role
$47.3K manager median
A replacement retail supervisor changes passive-owner economics materially; the base case assumes the owner performs the management role.
5
Reimbursement and collections
80/20 Medicare split
For covered DME after the deductible, Medicare rules can split the approved amount between Medicare and beneficiary coinsurance, making documentation and collection timing important.
6
Fixed cost, debt, and acquisition
$25.5K/mo base
Base fixed overhead, marketing, and debt service total $25,500 a month before employee payroll, so weak sales cannot be solved by inventory margin alone.
Want to test these assumptions in a full medical supply store forecast?
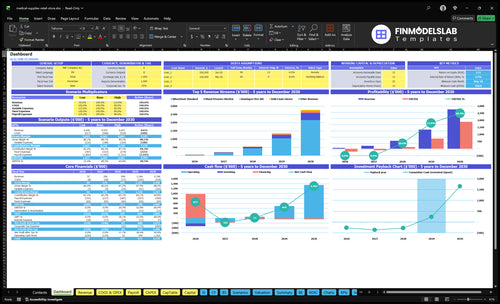
The Medical Supplies Retail Store Five-Year Financial Model Template lets you pressure-test revenue mix, product cost, payroll, capex, cash flow, and low/base/high scenarios. The dashboard preview is useful for checking whether owner-income assumptions still work when inventory, staffing, financing, and working-capital needs move together.
How much revenue does the store need to pay the owner $150K?
With the base cost structure, the store needs about $140,057 of monthly revenue, or $1.68M annualized, to support $12,500 of monthly owner income after the modeled 24% tax and 12% reinvestment reserves. Cash break-even before any owner take-home or reserves is lower: $57,500 of monthly modeled operating costs divided by the 55% gross margin equals roughly $104,545 of monthly sales. The gap between those two thresholds is what funds a real owner return rather than merely keeping the doors open.
Debt service is one reason target-pay revenue sits above cash break-even. The base case uses $4,000 a month of principal-and-interest service. SBA guidance notes that most 7(a) term loans are repaid with monthly principal and interest; see the SBA 7(a) loan guidance. The model treats principal-and-interest as a cash planning outflow because principal reduces cash even though it is not a GAAP operating expense.
Base revenue build
Planning assumption: about 30 consumer orders a day, 26 selling days a month, at a $140 blended ticket produces about $109,200.
Recurring refills, rentals, clinic accounts, and other B2B orders add about $40,800.
Total monthly sales land at $150,000; the model does not assume every dollar comes from walk-in traffic.
What this estimate hides
A product mix shift toward commodity supplies can lower margin even if transaction count rises.
A large clinic contract can improve volume but worsen receivable timing or require more inventory on hand.
A second delivery employee or full-time manager can move the target-revenue line upward immediately.
Can a medical supply store run without the owner?
Yes, but the owner should expect lower distributions unless sales are high enough to absorb a replacement manager. BLS reports a May 2024 median annual wage of $47,320 for first-line supervisors of retail sales workers, while retail salespersons had a $16.62 median hourly wage. Those national figures are starting points, not location-specific hiring quotes; see the BLS supervisor wage data and BLS retail salesperson data.
If the base store adds about $4,600 a month for a manager wage plus payroll burden, monthly labor rises from $32,000 to $36,600. With other inputs unchanged, annual owner income after reserves falls from $192,000 to about $156,672. That difference is the economic cost of replacing work the owner performed, not a penalty for absentee ownership.
Employee payroll stays at the base $32,000 monthly assumption.
The $192,000 residual mixes compensation for owner labor with return on invested capital.
Manager-run case
Add market-rate management payroll and enough authority to handle purchasing, service failures, and compliance tasks.
Require weekly reporting on margin, aged claims, inventory, payroll, and cash rather than only top-line sales.
Do not call a draw passive income until the business can operate without unpaid owner labor.
Key Takeaways
The base model turns $1.8M of annual revenue into $192,000 of owner income after modeled tax and reinvestment reserves, not before them.
Cash break-even is about $104,545 a month, but about $140,057 a month is needed to fund a $12,500 monthly owner target under the base reserve assumptions.
Owner labor has real replacement value; adding a manager can reduce distributions by tens of thousands of dollars even when sales do not change.
Margin, recurring orders, inventory days, reimbursement collections, payroll, and fixed financing commitments matter more than revenue alone.
How do reimbursement and inventory timing squeeze owner cash?
A medical supply store can show profit while having too little cash to distribute. For eligible Medicare Part B DME, after the deductible a beneficiary generally pays 20% of the Medicare-approved amount when the supplier accepts assignment; some equipment is rented rather than purchased. The Medicare DME coverage guidance shows why reimbursement creates billing and collection timing that cash retail does not.
CMS says Medicare DMEPOS suppliers must obtain accreditation, enroll, and post a surety bond; current guidance specifies $50,000 per NPI. See the CMS DMEPOS enrollment requirements. The bond amount is not an operating expense itself, but compliance still adds overhead and management time.
Inventory creates a second cash gap. Base direct product cost is $67,500 a month. At 60 days of inventory, about $135,000 is tied up; reducing average stock to 45 days frees about $33,750. That does not raise accounting profit immediately, but it can prevent borrowing to reorder fast-moving stock.
Weekly cash controls
Track inventory dollars and days on hand by category, not only total stock.
Separate cash sales, card settlements, Medicare receivables, commercial claims, and B2B invoices.
Age claims and invoices by 0-30, 31-60, 61-90, and over 90 days.
Pricing is not fully yours
Private-pay products can be repriced quickly; reimbursed items may be constrained by payer fee schedules and assignment rules.
CMS updates DMEPOS payment policies and fee schedules annually, so old reimbursement assumptions can become stale.
A claim denial can turn a booked sale into a working-capital problem unless documentation is complete.
What do low, base, and high owner-income cases look like?
The cases below use the exact calculator presets and raise payroll, marketing, and overhead as sales scale. They are planning cases, not an industry forecast: annual owner income after modeled reserves is $29,400 low, $192,000 base, and $405,360 high. Demand is not automatic; BLS Consumer Expenditure data show average household spending on medical supplies was $233 in 2024 versus $267 in 2023. See the 2024 BLS Consumer Expenditure release.
Low, base, and high planning cases
Compare one coherent set of sales, margin, staffing, overhead, debt, and reserve assumptions.
Medical Supply Store owner-income scenarios after modeled tax and reinvestment reserves.
Scenario dimension
Low CaseConservative
Base CasePlanning
High CaseUpside
Launch modelMonthly revenue and margin
$105,000 monthly revenue
50% product gross margin
Owner-led lean operation
$150,000 monthly revenue
55% product gross margin
Owner manages the store
$235,000 monthly revenue
58% product gross margin
Broader recurring and B2B book
Typical setupOrders and channels
About 24 daily consumer orders
$130 planning ticket
About $24,000 recurring and B2B sales
About 30 daily consumer orders
$140 planning ticket
About $40,800 recurring and B2B sales
About 42 daily consumer orders
$160 planning ticket
About $60,000 recurring and B2B sales
Cost driversMonthly cash assumptions
$27,000 labor
$15,000 fixed overhead
$3,500 marketing
$3,500 debt service
$32,000 labor
$16,500 fixed overhead
$5,000 marketing
$4,000 debt service
$47,000 labor
$20,000 fixed overhead
$8,000 marketing
$5,000 debt service
Owner income rangeAfter modeled reserves
$29,400After 20% tax + 10% reinvestment reserves
$192,000After 24% tax + 12% reinvestment reserves
$405,360After 26% tax + 14% reinvestment reserves
Best fitHow to use the case
Stress-test a slower ramp, commodity-heavy mix, and minimum fixed costs.
Plan a stabilized owner-operated store with balanced consumer, repeat, and B2B sales.
Test stronger demand only with the extra payroll, marketing, inventory, and overhead required to support it.
!
Planning note: These scenario figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, or distribution forecasts.
Which six income drivers matter most for a Medical Supply Store?
Owner income is most sensitive to product mix and gross margin; order volume, ticket, and repeat sales; inventory cash cycle; labor and owner role; reimbursement and collections; and fixed cost, debt, and customer acquisition. Strong sales still fail to become distributions if margin is weak or inventory and receivables absorb the cash.
1. Product mix and gross margin
Price the basket, not just the hero item
The base model uses a 55% product gross margin after merchandise, inbound freight, card fees, and other non-labor direct costs. That is a planning assumption, not a published small-store average. As an adjacent scale check, AdaptHealth reported 2025 product-and-supply cost at 39.9% of revenue while labor was reported separately at 23.1%; its delivery and payer mix make it unsuitable as a direct store benchmark. Review the 2025 cost-of-revenue breakdown.
At $150,000 monthly sales, 55% margin creates $82,500 of gross profit. A five-point drop to 50% removes $7,500 a month, or $90,000 a year before reserves. Category mix, discounts, returns, and vendor terms therefore move owner cash faster than small overhead cuts.
Track contribution by category
Manage gross-profit dollars, not only sales.
Net sales and product cost by category.
Returns, freight, card fees, and write-offs.
Gross profit dollars per order.
Vendor rebates and discount leakage.
Cut promotion on categories that grow revenue without funding payroll or owner cash.
2. Orders, ticket, and repeat sales
Build revenue from units the store can actually serve
The $150,000 base case can be pictured as about 30 consumer orders per selling day for 26 days at a $140 blended ticket, or $109,200, plus roughly $40,800 of recurring, rental, refill, referral, and clinic-account revenue. Those are planning units, not an industry average. Viemed, an adjacent home-medical-equipment operator, reported strong 2025 equipment-and-supply growth tied partly to resupply programs; use that only as evidence that replenishment can improve revenue quality, not as a retail growth benchmark. See its 2025 revenue mix discussion.
At 55% margin, another $10,000 of sales adds $5,500 of gross profit before added labor, delivery, and marketing. If those costs rise $4,500, only $1,000 remains before reserves.
Watch the revenue units
Separate demand into pieces that can be diagnosed weekly.
Consumer orders per day and blended ticket.
Recurring, refill, rental, and B2B revenue share.
Gross profit per acquired customer.
Repeat sales within 90 days.
Volume is valuable only when contribution survives the capacity it consumes.
3. Inventory cash cycle
Protect cash without starving the shelf
Base direct product cost is 45% of $150,000 monthly sales, or $67,500. Holding 60 days of that cost implies about $135,000 of inventory; reducing average stock to 45 days frees roughly $33,750 of working capital. That improves cash, not immediate accounting profit. The risk is cutting fast movers so deeply that stockouts lose repeat customers or referral sources.
SBA 7(a) working-capital guidance discusses financing tied to receivables or inventory and the need for current financial, receivable, payable, and inventory reporting. Those controls are useful even without a loan. See the SBA working-capital guidance.
Measure cash tied up by SKU family
Distributions should be tested after the next reorder cycle.
Inventory days by category.
Stockouts on repeat items.
Dead stock over 90 and 180 days.
Vendor terms versus sell-through.
A bank balance needed for the next vendor payment is not surplus owner cash.
4. Labor and owner role
Model the work even when the owner does it
Base employee labor is $32,000 a month and excludes the owner. BLS reported a May 2024 median hourly wage of $16.62 for retail salespersons and a $47,320 median annual wage for first-line retail supervisors. Medical supply work can require more billing, delivery, fitting, or product knowledge than generic retail, so local quotes may be higher. See BLS retail wage data.
Adding $4,600 of monthly manager payroll to the base case reduces annual owner income after reserves from $192,000 to about $156,672. That gap is the economic value of work the owner was doing, not passive investment return.
Schedule to gross profit
Track labor against contribution, not habit.
Gross profit per paid labor hour.
Owner hours by function.
Billing and delivery labor per order.
Revenue threshold for the next hire.
Rerun the target-pay revenue calculation before adding management payroll.
5. Reimbursement and collections
Treat payer mix as a cash-flow variable
For eligible DME under Medicare Part B, a beneficiary generally pays 20% of the Medicare-approved amount after the deductible when the supplier accepts assignment; equipment may be rented or purchased under program rules. See the Medicare DME coverage page. CMS also updates DMEPOS payment policy: its 2026 DMEPOS fee schedule update took effect January 1, 2026.
If $35,000 of monthly sales is reimbursement-based and collection stretches by 30 days, about $35,000 more can sit in receivables. Profit may be unchanged while the owner must delay a draw or use credit.
Run a claims dashboard beside the P&L
Review collections before distributions.
Days in receivables by payer.
First-pass acceptance and denial rate.
Unbilled orders awaiting documentation.
Cash-pay, Medicare, commercial, and B2B mix.
Rising sales with rising aged receivables is a cash warning.
6. Fixed cost, debt, and customer acquisition
Know the cost floor before buying growth
The base store carries $16,500 of fixed overhead, $5,000 of marketing, and $4,000 of debt service each month before employee payroll. Fixed overhead is a planning assumption covering rent, utilities, insurance, software, compliance administration, accounting, maintenance, and delivery support. CMS requires Medicare-reimbursed DMEPOS suppliers to obtain accreditation, enroll, and post a surety bond; current guidance states $50,000 per NPI. See the CMS enrollment guidance. The bond amount itself is not a $50,000 expense.
At the base reserve percentages, another permanent $1,000 of monthly cost cuts owner cash by about $640 a month, or $7,680 a year after modeled reserves.
Set a hard distribution gate
Pay the owner only after the next operating cycle is funded.
Four-week payroll, rent, debt, and vendor forecast.
Marketing cost versus 90-day gross profit.
Minimum cash after the next inventory reorder.
Upcoming compliance, vehicle, and equipment renewals.
Safe distributions are residual cash after commitments, not simply reported profit.
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Medical Supply Store Bundle
Choosing a selection results in a full page refresh.