Does Owner Income in a Speech Therapy Clinic Depend More on Volume or Margin?
Speech Therapy Clinic Bundle
An owner-operated U.S. speech therapy clinic can realistically produce about $51,000 to $192,000 a year of owner income in the planning cases modeled here, with a base case of $126,396. The base model assumes an owner-clinician plus three hired speech-language pathologists, about 450 collected visits per month, $130 of average collected revenue per visit, $58,500 of monthly revenue, and a 94% non-labor gross margin. Hired clinician payroll is the largest constraint, followed by rent and administration, marketing, debt service, and the cash reserve needed for taxes and reinvestment. The $126,396 figure is cash remaining after the model's 24% tax reserve and 8% reinvestment reserve; it is not a guaranteed salary, does not promise a distribution, and excludes entity-specific tax planning, retirement contributions, owner health benefits, and major capital purchases beyond the modeled reserve.
Owner income$126KNet margin18%Revenue for target pay$692KBusiness difficultyHard
What does the owner-income math look like for a speech therapy clinic?
The cleanest revenue unit is a collected visit, not an appointment booked. In the base case, 450 collected visits per month at a $130 blended collection produce $58,500 of monthly revenue. That collection assumption is deliberately treated as a planning value rather than a national reimbursement benchmark: 2026 Medicare national non-facility rates shown in the ASHA Medicare fee schedule include $76.15 for individual speech-language treatment and $226.46 for a speech-and-language evaluation, while commercial contracts and self-pay rates vary materially by market and payer.
Payroll is modeled separately from gross margin. That matters because the 2025 ASHA health care salary survey reported a $83,000 median full-time salary in outpatient clinics and offices. The base case uses three hired SLPs plus front-office support inside $28,500 of monthly labor expense, while the owner remains clinically active and is not counted in payroll. The owner's residual cash therefore blends compensation for clinical work with the entrepreneurial return from owning the practice.
Owner income calculator
Estimate owner take-home from collected revenue, clinic costs, reserves, and a target monthly pay level.
!
Planning note: Research-based planning estimate only. It is not guaranteed salary, tax advice, or owner distribution advice.
1
Collected visits
450 / month
Completed, documented, and collected visits set the base revenue volume; twenty missed collections a month can remove roughly $20,000 of annual owner cash.
2
Average collection
$130 / visit
The base blended collection is a planning assumption across treatment, evaluation, payer, and self-pay mix; a $10 drop can materially compress owner income.
3
Clinician payroll
$28.5K / month
Three hired SLPs plus support make labor the largest cash cost in the base case, before any owner salary or distribution is counted.
4
Schedule utilization
About 26 visits / clinician-week
The base case needs each of four treating clinicians, including the owner, to average about 26 collected visits per week after cancellations and nonbillable work.
5
Cash conversion
$58.5K = one month of sales
If collections slip by one month, a full month of base revenue can sit outside the bank account even while the profit-and-loss statement looks healthy.
6
Owner clinical role
About $8.6K loaded replacement / month
Replacing the owner-clinician with a hired SLP at the survey median plus a 25% loading sharply reduces residual cash unless revenue also scales.
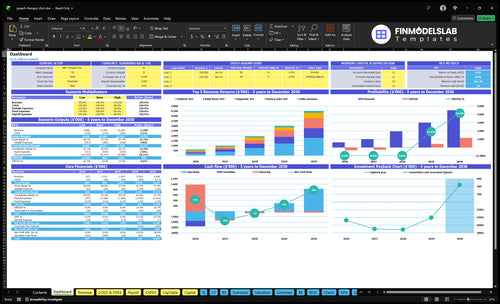
Want to test the clinic assumptions in a full forecast?
The dashboard preview helps test patient volume, collected rate, staffing, operating costs, runway, and cash-flow timing together. The Speech Therapy Clinic Financial Model Template in Excel can be useful when you want those assumptions tied to statements and multi-year scenarios rather than viewed as a single owner-income month.
How many patient visits does a clinic need to support $10,000 a month in owner pay?
Under the base cost structure, the clinic needs about $57,666 of monthly revenue to support a $10,000 monthly owner-pay target after the 24% tax reserve and 8% reinvestment reserve. At the modeled $130 average collection, that is about 444 collected visits per month, or roughly 102 per week. With four treating clinicians, including the owner, the target is about 25 to 26 collected visits per clinician per week. That workload is a planning assumption, not a payer or clinical standard; ASHA's productivity guidance notes that employers commonly track patient-care productivity while also recognizing documentation, care coordination, family training, and other required nonbillable work.
Break-even before owner pay
Base operating costs are $39,500 per month.
At a 94% gross margin, operating break-even is about $42,021 of monthly revenue.
At $130 per collected visit, that is about 323 visits per month.
Break-even is not the same as a safe owner distribution because reserves and target pay still come afterward.
Target-pay capacity
The $10,000 monthly target pushes needed revenue to $57,666.
The base case at $58,500 clears that target by only $533.
Twenty fewer collected visits would cut monthly revenue by $2,600 at the base collection rate.
A clinic operating near the target therefore needs a cancellation, referral, and wait-list plan rather than relying on gross appointment capacity.
Demand may be supportive, but capacity still has to be converted into attended care. The 2025 ASHA caseload report found that 41% of surveyed clinical service providers reported larger caseloads since January 2024, while 32% worked in private practice. Separately, the BLS Occupational Outlook Handbook projects 15% growth in SLP employment from 2024 to 2034. Neither statistic guarantees a local waiting list, so the owner should track referral-to-evaluation conversion and completed visits, not just national demand.
Can the owner step out of patient care and keep the same income?
Usually not at the same revenue level. The base case is explicitly owner-operated: the owner treats patients while three hired SLPs and support staff sit inside payroll. ASHA's 2025 outpatient-clinic median salary was $83,000, and ASHA notes that employer cost can run about 1.25 to 1.4 times salary once payroll taxes, benefits, retirement, and related overhead are included. Using the low end of that loading, replacing the owner-clinician adds about $8,646 a month of labor cost.
If the owner keeps treating
Base owner income is $126,396 after modeled reserves.
The output includes the economic value of the owner's clinical labor.
Owner pay is not duplicated inside the $28,500 employee payroll line.
The owner can shift some time to supervision or growth only if the schedule still supports collected-visit targets.
If the owner hires a replacement
Adding roughly $8,646 of loaded monthly SLP cost raises operating costs to about $48,146.
At unchanged $58,500 revenue, modeled annual owner income falls to about $55,836 after reserves.
This estimate still does not include a separate full-time general manager.
Passive ownership therefore requires more scale, higher collections, tighter overhead, or both.
This is also why salary and distribution should be discussed separately. An owner who performs full-time clinical work is doing a job the clinic would otherwise have to buy in the labor market. The BLS wage data show a May 2024 median wage of $98,470 for SLPs in offices of physical, occupational and speech therapists, and audiologists. The residual cash above a reasonable market value for the owner's labor is closer to an entrepreneurial return; the exact split between W-2 salary, draw, and distribution depends on entity structure and tax advice.
How do insurance rates, cancellations, and collections change take-home?
Small changes in the collected dollars per visit can move owner income faster than they move revenue. The 2026 national Medicare fee table lists $76.15 for individual speech-language treatment and $226.46 for a speech-and-language evaluation, and ASHA's private-practice Medicare guidance explains that Medicare Part B payment is tied to the Physician Fee Schedule and specific procedure codes. Commercial payer contracts, Medicaid, self-pay, and evaluation mix can be very different, so the model uses $130 only as a blended planning assumption.
$10 less collected per visit
450 visits at $120 instead of $130 reduce monthly revenue from $58,500 to $54,000.
At the same 94% gross margin and operating costs, annual owner income falls from $126,396 to about $91,884.
The $10 pricing or payer-mix move therefore costs about $34,512 of annual owner income in this model.
Track actual allowed amount and patient responsibility by payer, not the clinic's posted fee schedule.
Twenty fewer collected visits
Twenty missed collections remove $2,600 of monthly revenue at $130 per visit.
With fixed costs unchanged, modeled annual owner income falls to about $106,452.
No-shows, delayed authorizations, incomplete documentation, and claim denials all reduce collected volume even when calendars look full.
Use completed-and-collected visits as the operating KPI that connects the schedule to cash.
Self-pay adds a different compliance obligation. CMS says uninsured or self-pay patients generally must receive a good faith estimate of expected charges before scheduled care, so clinics should align pricing, intake, and billing workflows with current CMS good-faith-estimate guidance. The financial point is simple: quoted price is not owner income. The amount has to be scheduled, clinically delivered, documented, billed correctly, collected, and then reduced by payroll and overhead.
What has to be paid before an owner distribution is actually safe?
In the base month, $58,500 of revenue becomes $54,990 of gross profit after the 6% non-labor direct-cost allowance. The clinic then pays $28,500 of hired labor, $7,500 of fixed overhead, $2,000 of marketing, and $1,500 of debt service, leaving $15,490 before reserves. The model then holds back $3,718 for tax and $1,239 for reinvestment, leaving $10,533 of monthly owner income. That sequence is the difference between accounting profit and cash that is actually safer to distribute.
Revenue is collections before costs. Accounting operating profit or EBITDA is not the same as an owner draw or distribution: a draw transfers cash after profit is earned. This calculator is a cash bridge, not EBITDA, because debt service is deducted before its profit-before-reserves output.
Cash can be tighter than the profit-and-loss statement suggests. One month of base revenue outstanding means $58,500 has not reached the bank while payroll, rent, and debt are due; two months represents $117,000. These are planning examples, not claims-timing benchmarks.
Compliance belongs in overhead. HHS says providers conducting covered electronic transactions can be HIPAA covered entities with privacy, security, and business-associate duties; see the HHS covered-entity guidance. Licensing is also non-optional. Underfunding credentialing, secure systems, or documentation can interrupt billing and create expensive risk.
The tax reserve is not a tax calculation. The IRS self-employed tax center explains that people in business for themselves generally file annual returns and may need estimated tax payments during the year. The article's 24% reserve is only a cash-planning assumption; actual federal, state, payroll, and entity-level tax treatment can be higher or lower. The reinvestment reserve is equally deliberate: it keeps some cash inside the clinic for assessment materials, technology, clinician recruitment, repairs, and claims-cycle volatility before the owner decides what to distribute.
Key Takeaways
The base owner-operated clinic produces $126,396 of annual owner income after modeled tax and reinvestment reserves, not before them.
About $692,000 of annualized revenue is needed to support the base $10,000 monthly owner-pay target under the modeled cost structure.
Hired SLP payroll and the owner's own clinical contribution are the two biggest reasons owner income changes as the clinic scales.
Safe distributions should follow debt service, payroll, compliance overhead, tax reserves, reinvestment needs, and a realistic allowance for receivables.
What do low, base, and high owner-income cases look like?
The three cases change volume, staffing, overhead, marketing, debt, and reserves together. The low case is not simply the base clinic with lower sales; it carries minimum fixed costs and two hired clinicians. The high case adds another hired clinician, higher facility and administrative overhead, more marketing, and a larger reserve rate. Owner income below is after the calculator's modeled tax and reinvestment reserves.
Owner income scenarios
Three coherent operating cases tied to the calculator presets.
Low, base, and high planning cases for an owner-operated outpatient speech therapy clinic.
Scenario factor
Low CaseLean
Base CaseBase
High CaseScale
Launch modelClinical capacity
Owner + 2 hired SLPs
About 320 collected visits/month
Owner + 3 hired SLPs
About 450 collected visits/month
Owner + 4 hired SLPs
About 625 collected visits/month
Typical setupRevenue and margin
$38,000 monthly revenue
93% gross margin
$8,000 target owner pay
$58,500 monthly revenue
94% gross margin
$10,000 target owner pay
$85,000 monthly revenue
95% gross margin
$15,000 target owner pay
Cost driversMonthly cash load
$19,000 labor
$10,500 other operating costs
$28,500 labor
$11,000 other operating costs
$41,000 labor
$14,300 other operating costs
Owner income rangeAfter modeled tax and reinvestment reserves
$51,156
$126,396
$192,396
Best fitOperating posture
Slower referral ramp
Tight owner cash
Owner-operated
Stable four-clinician capacity
Five treating clinicians
Higher support cost and reserves
!
Planning note: Scenario figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, or distribution forecasts.
Which six drivers matter most for speech therapy clinic income?
Owner income is most sensitive to six linked operating decisions: collected visits, average collection per visit, clinician payroll, schedule utilization, cash conversion, and the owner's clinical role. The order matters because each later decision sits on top of the revenue and labor economics created by the earlier ones.
1. Collected visits
Measure care that turns into cash
The base case needs 450 collected visits a month, about 104 per week or 26 per treating clinician across the owner and three hired SLPs. Count completed, documented, collectible care rather than open calendar slots; cancellations, authorization gaps, and denials can make a full-looking schedule miss the revenue target.
Losing 20 collected visits at $130 removes $2,600 of monthly revenue and drops modeled annual owner income from $126,396 to about $106,452. The BLS outlook projects strong SLP employment growth, but local referrals still have to become attended, billable visits.
Track the visit funnel every week
A weekly dashboard should show the path from referral to collection so the owner can see where capacity leaks before month-end.
New referrals received
Evaluations scheduled and completed
Treatment visits completed
Cancellation and no-show rate
Collected visits by clinician
2. Average collection per visit
Model payer mix with collected dollars, not sticker price
The $130 base collection is a planning assumption across different services and payers. In the 2026 national Medicare schedule, individual speech-language treatment is $76.15 while the combined speech-sound and language evaluation code is $226.46. Those are not commercial-market averages, but they show why service mix changes the blended collected rate.
A $10 decline in the blended collection takes monthly revenue from $58,500 to $54,000 and modeled annual owner income to about $91,884. Track allowed amount, patient responsibility, denials, and payment timing by payer instead of treating billed charges as revenue.
Watch net collection by payer and code
Use actual remittance data to update the model rather than leaving the $130 assumption untouched.
Average collected dollars per completed visit
Evaluation mix versus treatment mix
Top payer allowed amounts
Patient-responsibility collection rate
Contractual write-offs and denials
3. Clinician payroll
Hire only when a schedule can carry the loaded cost
Payroll is the base clinic's largest cash expense at $28,500 per month. ASHA reported a $83,000 outpatient-clinic median salary, while its productivity resource says employer cost can reach about 1.25 to 1.4 times salary. At the low end, that is roughly $103,750 a year, or $8,646 a month, per SLP.
At $130 per visit and a 94% gross margin, about 71 collected visits produce $8,674 of monthly gross profit, barely covering the $8,646 loaded clinician cost before extra room, software, or administration. Hire against a durable wait list that can support more than that threshold.
Use a clinician contribution scorecard
Separate clinical productivity from clinical quality and track whether each added FTE is financially mature.
Loaded labor cost per clinician
Collected visits per FTE
Collected revenue per FTE
Gross profit before allocated overhead
Time from hire to break-even caseload
4. Schedule utilization
Protect billable capacity without pretending every hour is billable
The base case needs about 26 collected visits per treating clinician per week, leaving time for documentation, care coordination, authorization work, and cancellations. ASHA emphasizes that patient-care activity extends beyond face-to-face billable time, so budgeting every paid hour as billable will overstate owner income.
The base clinic spends $2,000 per month on referral development and patient acquisition. That spend works only if it fills usable capacity. Referral relationships, recall systems, and a cancellation wait list can raise collections when open slots actually exist.
Track usable capacity, not theoretical capacity
Compare scheduled demand with the slots that can realistically produce care after documentation and clinical constraints.
Collected visits per clinician-week
Booked-to-completed conversion
Same-week cancellation refill rate
Wait-list depth by preferred time
Marketing cost per first completed evaluation
5. Cash conversion and overhead discipline
Keep profit from being trapped in receivables
The base model carries $7,500 of fixed overhead, $2,000 of marketing, and $1,500 of debt service before owner cash. One month of base sales is $58,500; two months is $117,000. That shows the liquidity exposure if receivables build while payroll and rent still come due.
Overhead also includes systems needed to bill responsibly. HHS explains that covered providers have HIPAA obligations and may need business-associate arrangements with vendors. Underfunding secure systems or billing support can save a small line item while increasing denial and compliance risk.
Run a cash dashboard beside the P&L
Profit tells you whether the model works economically; cash metrics tell you whether the clinic can make payroll while waiting to collect.
Accounts receivable balance
Days from service to claim submission
Days from claim to payment
Denial and resubmission rate
Cash reserve in months of operating cost
6. Owner clinical role and management leverage
Decide whether the owner is buying a job, building a practice, or both
The owner is one of four treating clinicians and is excluded from employee payroll, so $126,396 is not a passive distribution. Replacing that clinical capacity with an SLP costing about $8,646 a month reduces modeled annual owner income to about $55,836 at unchanged revenue; a separate manager would reduce it further.
A less owner-dependent clinic needs enough scale to pay for replacement clinical and managerial labor. Licensure also constrains geographic expansion: BLS says all states require SLP licensure, and ASHA's state-by-state resource tracks licensure, supervision, telepractice, and continuing-education rules. Model multi-state telepractice against those requirements and payer contracts.
Separate owner labor from owner return
Price the jobs the owner performs, then measure the business return left after the practice could replace those jobs.
Owner clinical hours per week
Owner administrative hours per week
Loaded replacement cost for each role
Owner income after modeled reserves
Residual profit after replacement labor
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Choosing a selection results in a full page refresh.