How Do Location and Scale Affect the Startup Costs of a Healthcare Clinic?
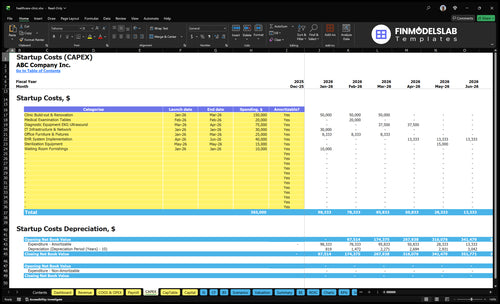
This US planning guide separates $365,000 of clinic CAPEX from pre-opening expenses, monthly operating costs, and the $788,000 minimum cash need shown in Month 2 The model covers the first operating year through early ramp-up, with Month 1 breakeven and Year 1 EBITDA of $930,000 These are researched planning assumptions, not vendor quotes or guaranteed costs
Estimate Startup Costs with Calculator
Startup CAPEX Calculator
Estimates capitalized startup assets only for a healthcare clinic opening across Month 1 to Month 6.
!
Excluded from CAPEX Base CAPEX is $365k across Month 1 to Month 6. This calculator excludes inventory, payroll runway, rent deposits, insurance premiums, debt service, working capital, marketing, loan payments, and monthly software subscriptions.
What does this Healthcare Clinic model screenshot show?
What hidden costs of opening a healthcare clinic should founders budget?
Founders opening a Healthcare Clinic need cash beyond equipment and buildout; hidden costs like payer credentialing, compliance setup, pre-opening payroll, billing setup, supplies, drugs, and delayed reimbursements can hit before revenue starts. For a quick benchmark, monthly fixed costs already include $25k malpractice insurance, $500 licensing and regulatory fees, $12k IT support and software subscriptions, and $10k lease payment. If you want the owner-side picture, see How Much Does The Owner Of Healthcare Clinic Make? because Year 1 admin payroll is $235k before provider pay, and the minimum cash need is $788k in Month 2.
Hidden startup costs
Payer credentialing delays slow cash
Malpractice deposits hit before launch
Legal and accounting help adds cost
Billing setup and compliance cost cash
Cash you must plan for
Pre-opening payroll starts before revenue
Initial supplies and pharmaceuticals need stock
Admin payroll reaches $235k in Year 1
Cash need reaches $788k in Month 2
How should healthcare clinic startup funding connect to financial projections?
Healthcare Clinic funding should map cleanly to CAPEX, startup costs, and the cash trough from ramp-up. With 7 Year 1 clinicians, $365k CAPEX, $169k monthly fixed overhead, $235k Year 1 admin payroll, and a $788k minimum cash need in Month 2, the raise has to cover the build and the burn. Here’s the quick math: use monthly treatments, price per treatment, and provider capacity to prove revenue, so a general practitioner at 400 monthly treatments, $100 per treatment, and 60% Year 1 capacity gives lenders a real ramp.
Funding uses
$365k CAPEX timing
Startup expenses by month
7 Year 1 clinicians
$235k admin payroll
Model proof points
$169k fixed overhead monthly
$788k Month 2 cash need
Show EBITDA and breakeven
Show payback and cash trough
Revenue assumptions should connect monthly treatments, price per treatment, and capacity, not just a yearly guess. Lender-ready projections need to show collections timing too, because fee-for-service cash often lands after the visit.
Revenue ramp
Use monthly treatment counts
Use price per treatment
Use provider capacity
Use Year 1 ramp
Bank asks
Show cash runway base model
Show CAPEX and overhead
Show collections timing
Show breakeven and payback
What drives healthcare clinic buildout costs?
Healthcare Clinic buildout costs are driven less by rent and more by what the space is missing: plumbing, exam room count, ADA access, reception flow, waiting room space, storage, infection control workflow, signage, and local code fixes. The model uses $150k for clinic build-out and renovation in Months 1 to 3, plus $25k for office furniture and fixtures and $10k for waiting room furnishings, so initial facility CAPEX is $185k. Here’s the quick math: the cheapest lease can become the most expensive site if walls, plumbing, and compliance work are not already in place.
Main cost drivers
Space condition sets the base cost.
Square footage drives finish work.
Exam rooms raise build complexity.
Plumbing can move the budget fast.
Model CAPEX
$150k build-out and renovation.
$25k office furniture and fixtures.
$10k waiting room furnishings.
$185k total facility CAPEX.
Calculate Fuding Needs
Startup cost summary
This table splits clinic startup spend into CAPEX and excluded launch cash so you can see what gets funded upfront.
Highlighted CAPEX$320,000Base planning example
Excluded cash needs$788,000Outside CAPEX total
Funding need$1,108,000CAPEX + excluded cash needs
Cost Category
Base Estimate
Main Cost Driver
CAPEX Calculator
Clinic Build-out & Renovation
$150,000
Leasehold work and room fit-out size
Yes
Diagnostic Equipment EKG Ultrasound
$75,000
Scope of imaging and testing equipment
Yes
EHR System Implementation
$40,000
System setup, data migration, and launch support
Yes
IT Infrastructure & Network
$30,000
Network, hardware, and clinic connectivity
Yes
Office Furniture & Fixtures
$25,000
Waiting and admin area furnishing scope
Yes
Operating Reserve
$788,000
Month 2 cash trough from fixed payroll, lease, and insurance before ramp
No
Healthcare Clinic Core Five Startup Costs
Facility Buildout And Leasehold Improvements Startup Expense
Buildout Base
Facility buildout is CAPEX, not a monthly expense. Use $150k for clinic build-out and renovation across Months 1–3, plus $25k for office furniture and fixtures and $10k for waiting room furnishings. This covers reception, exam rooms, ADA access, plumbing, storage, signage, life safety, and local code compliance.
Scope Inputs
Size the estimate from the leased space, not a guess. Ask about the number of exam rooms, wet-room needs, landlord allowance, inspection requirements, and whether the layout supports 7 Year 1 clinicians. If the shell is rough or plumbing is missing, the buildout can move fast. Keep the scope tied to clinical flow.
Check leased space condition
Count exam rooms needed
Confirm inspection rules
Keep Scope Lean
Control cost by locking the layout before bids and separating code work from finish work. Don’t cut ADA, life safety, or inspection items. The clean savings come from avoiding late changes, oversizing storage, or adding waiting room finish work that does not help patient flow or provider capacity.
Get two contractor quotes
Freeze the floor plan early
Delay nice-to-have finishes
Budget Fit
Use the buildout as the fixed opening base. With $150k in renovation plus $35k in related furniture and waiting room items, the facility line is $185k before equipment, IT, licensing, and staffing. If the lease already has compliant plumbing and finish work, this number drops; if not, it rises quickly.
Medical Equipment And Exam Room Setup Startup Expense
Base Gear
For outpatient care, split the spend into base room setup and specialty gear, not hospital-scale units. The base room setup covers exam tables, vital signs tools, procedure supplies, and refrigeration if needed. The source CAPEX is $20k for medical examination tables, $75k for electrocardiogram (EKG) and ultrasound, and $15k for sterilization, or $110k total.
Estimate
Build the estimate from rooms, service mix, and timing. Use units × unit price for tables, diagnostic tools, and sterilizers, then add quotes for maintenance planning. General practice and nurse practitioner visits lean on base room setup; pediatrics, dermatology, and physiotherapy may need more specialty gear. Stage buys from Month 2 to Month 5.
Control
Keep purchases tied to what each room uses every day. Buy the base room setup first, then add specialty gear only when the schedule proves demand. The common mistake is overbuying hospital-level equipment. Plan service by service, and keep maintenance budgets beside the asset list so downtime does not hit visits.
Timing
The Month 2 to Month 5 window is when ordering, install, and testing should happen. That leaves time for room-by-room setup, staff training, and repair checks before go-live. If the mix skews to general practice and nurse practitioner visits, the package stays lighter; dermatology or physiotherapy pushes more specialty spend.
EHR, IT, Billing, And Admin Systems Startup Expense
Split the spend
Separate one-time setup from monthly software. Here, startup CAPEX includes $30k for IT infrastructure and network in Month 1 plus $40k for EHR, or electronic health record, implementation in Months 4 to 6. That gives $70k of setup before ongoing fees start.
What it covers
This budget covers computers, networking, cybersecurity, phones, patient portal, scheduling, billing workflows, payment systems, and staff training. The recurring layer adds 4% of Year 1 revenue for EHR and billing software fees, plus $12k monthly for IT support and software subscriptions.
Trim it safely
Keep the spend tight by pricing it by users, exam rooms, integrations, and whether billing stays in-house or goes outsourced. Fewer integrations and a simpler workflow cut build and support cost. Don’t underbuy cybersecurity or training; those gaps usually show up later as downtime, rework, or payment delays.
Budget driver check
Here’s the quick math: $70k is the setup base, then recurring cost scales with revenue and usage. The hidden risk is timing, since the Month 4 to Month 6 EHR rollout can overlap with launch work. If the clinic adds more users or rooms, support and training costs move up fast.
Licensing, Credentialing, Legal, And Insurance Startup Expense
What It Covers
Treat most of this as pre-opening expense, not an asset, unless you create a specific intangible. The base run rate is $500 a month for licensing and regulatory fees plus $25k a month for malpractice insurance from Month 1 through Month 60. It also covers state licensing, credentialing, payer enrollment, general liability, HIPAA compliance, legal setup, accounting support, and policy documents.
How To Estimate
Build the estimate from state rules, provider count, payer mix, and specialty mix. Add fee quotes for credentialing, enrollment, and insurance, then spread recurring coverage across 60 months. In the budget, this sits with launch costs, but it does not turn into revenue until payers are active.
Keep It Tight
Get quotes early and match coverage to the clinic's actual services. Do not overbuy specialty policies or assume every payer moves at the same speed. Credentialing delays can push cash collections later even when care starts, so track payer status weekly and keep extra working capital for the gap.
Timing Gap
If the clinic is clinically ready before enrollments clear, revenue can lag by weeks or months. That means the real risk is not just the fee line; it is the delay between opening doors and getting paid. Plan cash for that gap, especially with more providers or a heavier payer mix.
Staffing, Supplies, And Launch Operating Startup Expense
Payroll Setup
Payroll is launch working capital, not CAPEX. Year 1 admin staffing totals $235k annual pay for the clinic manager, 2 medical assistants, the receptionist, and the listed billing and janitorial roles. Build this into pre-opening cash so you can hire, train, and open without starving day-one operations.
Launch Supplies
Use opening cash for consumables: 6% of revenue for medical supplies and disposables, 3% for pharmaceuticals, 3% for outsourced diagnostics, and 4% for EHR and billing fees. That is 16% of revenue before rent and wages, so volume matters fast.
Stock for Month 1 to Month 3.
Price by service mix, not guesswork.
Reorder from usage, not fear.
Startup Cash
Cover recruiting, onboarding, uniforms, office supplies, medical consumables, and early marketing with working capital. If opening delays, these costs still hit cash. The clean rule: if it gets used up, it is an expense; if it lasts and has a long life, it is CAPEX.
Cash Buffer
The model also shows recurring fixed costs of $169k monthly before wages, so keep a launch buffer for slow patient ramp and delayed collections. A clinic can look open on paper and still run out of cash if payroll, supplies, and billing lag hit at the same time.
Compare 3 Startup Cost Scenarios
Startup cost scenarios
Clinic startup cost changes fast with room count, equipment depth, and staffing. Lean trims the launch; Base matches the model case; Full adds more space, more gear, and more cash.
Lean, Base, and Full clinic launch cost bands
Scenario
Lean LaunchSmaller opening
Base LaunchSource case
Full LaunchExpanded build
Launch model
Use a smaller site with fewer exam rooms, lighter diagnostic gear, a narrower service list, and a leaner first-year team.
Use the source-case clinic with 7 Year 1 clinicians, 5 service lines, and the modeled Month 2 cash need of $788k against $365k of CAPEX.
Use a larger site with more exam rooms, deeper diagnostic gear, broader hours, a wider service mix, and more working capital.
Typical setup
Smaller square footage, fewer exam rooms, fewer than 7 Year 1 clinicians, basic equipment, a shorter working capital runway, and only core outpatient visits.
Mid-size square footage, a standard exam-room setup, standard diagnostic equipment, $169k monthly fixed overhead, and $235k Year 1 admin payroll.
Larger square footage, more exam rooms, more than 7 Year 1 clinicians, deeper equipment, broader staffing, and a longer runway for ramp-up.
Cost drivers
Smaller build-out
lighter equipment
lower staffing
shorter runway
Build-out
standard equipment
fixed overhead
admin payroll
working capital
More rooms
deeper equipment
broader staffing
larger build-out
extra working capital
Planning rangeCAPEX only
$700,000 - $950,000Lower capital
$1.1M - $1.3MModeled baseline
$1.4M - $1.8MHigher capital
Best fit
Founders testing demand with one core site and a narrow service mix.
Operators ready to open the modeled outpatient mix with enough cash to cover ramp-up.
Teams with stronger demand proof, more funding, and a bigger site scope.
!
Planning note: These ranges are planning assumptions from the model, not vendor quotes; final numbers change with site size, build-out scope, equipment quotes, and lease terms.
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Healthcare Clinic Bundle
Choosing a selection results in a full page refresh.