

Revenue & Calc
Plan chair capacity, monthly utilization, service allocations, and net hourly fees. Revenue captures service assumptions; Calc converts the full launch month and subsequent periods into a 60-month revenue schedule.


The Dental Clinic Financial Model is an Excel financial planning template for projecting a general dental practice from patient-service capacity, realized fees, direct clinical costs, staffing, and startup investment. It converts editable operating assumptions into monthly calculations and annual financial projections for 2026 through 2030.
The illustrated case is a hypothetical, owner-operated dental clinic in suburban Columbus, Ohio, with two active chairs and four staffed roles. Its forecasts are planning scenarios, not observed practice results, guaranteed earnings, or published local benchmarks.
The workbook links clinical activity and fee assumptions to financial statements and decision-focused reporting, while keeping detailed inputs in their supporting schedules.
Plan chair capacity, monthly utilization, service allocations, and net hourly fees. Revenue captures service assumptions; Calc converts the full launch month and subsequent periods into a 60-month revenue schedule.
Separate clinical supplies, external laboratory and imaging costs from payment fees, patient acquisition, and fixed facility costs. Expense dates and spending frequency drive the monthly expense calculation.
Budget dentist, hygienist, assistant, and reception compensation by role. Record clinical equipment, fit-out, and other capital assets separately, with supporting expenditure and depreciation schedules.
Use CapTable for owner contributions, Debt for optional financing schedules, and Dashboard for model settings, working-capital days, and Low, Base, or High scenario multipliers.
Review the Income Statement, Cash Flow, Balance Sheet, and combined Summary. Workbook Checks compare linked schedules and flag potential input or reconciliation issues.
Dental practice revenue is calculated from one shared pool of occupied chair-hours, allocated across five services and multiplied by their net realized hourly fees.
Two chairs operating 20 clinical days per month for eight hours per day provide 320 available chair-hours monthly. Utilization rises from 50% in 2026 to 80% in 2030, so the illustrative case sells 160 to 256 occupied chair-hours per month.
The service allocation is 40% preventive hygiene, 25% fillings, 15% crowns and bridges, 10% emergency and extractions, and 10% periodontal hygiene. These shares total 100%, preventing the same occupied hour from being sold twice.
The Revenue Forecast connects chair counts, days, scheduled hours, utilization, service mix, and realized fees to projected patient-service revenue. Adjusting utilization or pricing flows into the monthly Calc schedule and the annual sales plan.
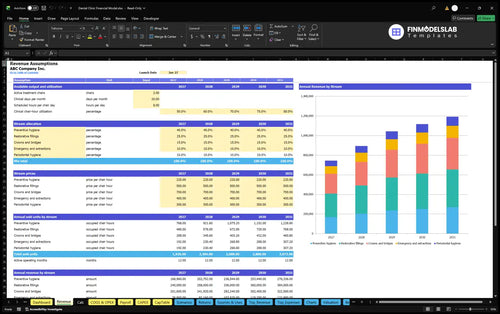
2 chairs × 20 days × 8 hours × 50% utilization × $388 blended realized fee per occupied hour × 12 months = $744,960.
The $388 blended fee comes from hourly prices of $220 for preventive hygiene, $500 for fillings, $700 for crowns and bridges, $400 for emergency work, and $300 for periodontal hygiene, weighted by their respective service shares.
The expense forecast separates revenue-linked clinical costs and variable overhead from monthly fixed expenses and annual base compensation, counting each cost once.
The COGS and Operating Expenses Forecast applies 6% clinical supplies, 7% external dental laboratory fees, and 0.5% external imaging to revenue. It also models 2.4% processing and billing fees, 4% patient acquisition, and fixed premises and administrative costs.
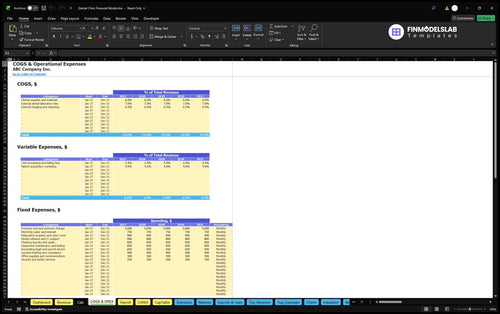
The illustrative 2026 case includes $100,570 in direct costs and $47,677 in variable expenses. Fixed operating costs total $126,000 per year, including $5,000 monthly rent and common charges alongside utilities, insurance, software, cleaning, maintenance, and compliance.
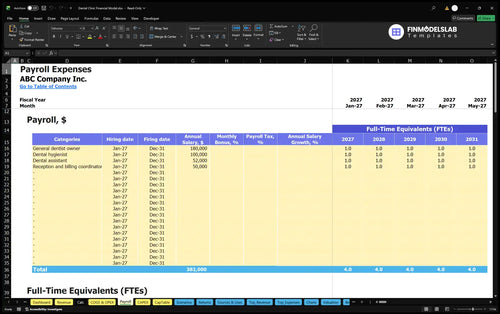
The Payroll Forecast plans staffing by role, FTE, salary, hiring dates, and related monthly personnel charges. This case includes a $180,000 dentist base, $100,000 hygienist base, $52,000 assistant base, and $50,000 reception and billing base annually.
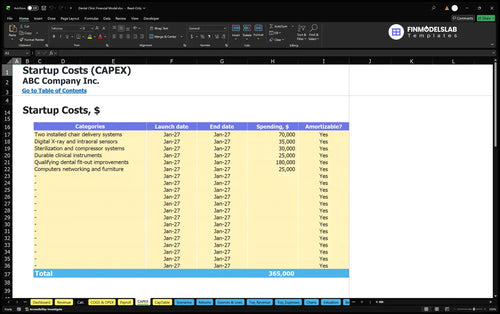
Startup equipment, preopening cash, working capital, and the contingency reserve are financing requirements rather than recurring operating expenses in the EBITDA calculation.
The case budgets $365,000 in qualifying startup assets, including chair systems, digital X-ray equipment, sterilization, instruments, fit-out, and other durable installations. It separately identifies $56,000 in opening cash uses such as deposits, permits, marketing, preopening services, and training.
The Capital Expenditure Plan records equipment and facility improvements by purchase amount and date, with supporting depreciation schedules. It distinguishes investment in durable dental assets from routine supply purchases and other operating charges.
Working-capital assumptions are 18 accounts-receivable days, 13 accounts-payable days, and 13 inventory days. The opening net working-capital estimate is $36,738, and the $164,062 reserve is designed around three months of recurring outflows, including base payroll.
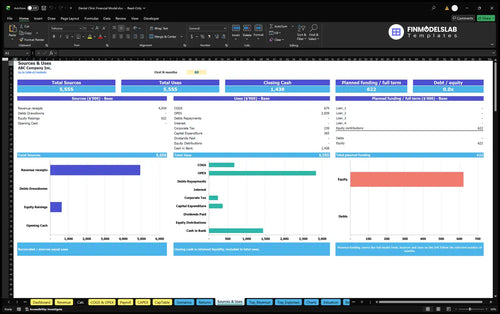
The Sources and Uses of Funds report reconciles contributions and other financing with cash allocated to startup investment, operations, and retained liquidity. The example assumes approximately $621,800 of initial owner funding, with no committed third-party borrowing.
The selected dental clinic case projects increasing EBITDA as occupied chair-hours rise, while base payroll and recurring fixed overhead remain constant in the operating assumptions.
| Year | Revenue | Operating Expenses | EBITDA |
|---|---|---|---|
| 2026 | $744,960 | $656,247 | $88,713 |
| 2027 | $893,952 | $685,896 | $208,056 |
| 2028 | $1,042,944 | $715,546 | $327,398 |
| 2029 | $1,117,440 | $730,371 | $387,069 |
| 2030 | $1,191,936 | $745,195 | $446,741 |
Illustrative planning case, not actual practice performance. Amounts are rounded to whole dollars; displayed differences can reflect rounding.
At 80% utilization in 2030, 256 monthly occupied chair-hours generate projected annual revenue of $1,191,936. Illustrative operating expenses are $745,195, leaving $446,741 of EBITDA before depreciation, financing costs, and income taxes.
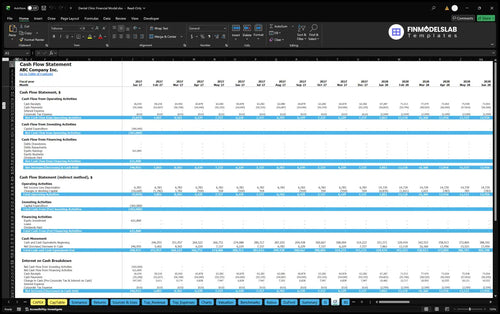
The Cash Flow Forecast translates operating activity, working-capital timing, capital purchases, and equity or debt movements into projected cash receipts and payments. This is where a buyer evaluates liquidity separately from the EBITDA shown in the operating forecast.
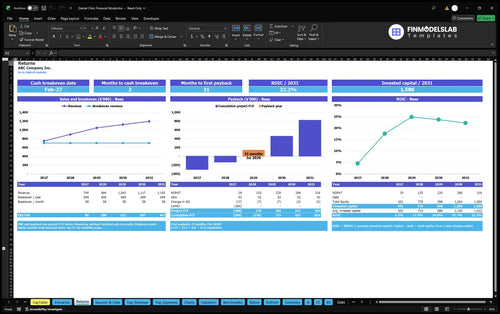
The declared Returns and scenario reports support distinct questions about operational coverage, recovery of invested cash, and the sensitivity of projected financial performance.
Sales break-even estimates the activity required to cover operating costs. Cash break-even concerns cash inflows and outflows, investment payback concerns cumulative recovery of invested funds, and annual ROIC measures return relative to invested capital; these are not interchangeable.
The Returns analysis presents sales break-even, cash break-even timing, investment payback, and return on invested capital as separate calculations. Use them to assess dental chair utilization requirements and capital recovery without treating annual EBITDA as a payback figure.
The Dashboard provides Low, Base, and High multipliers for revenue, direct costs, variable overhead, fixed expenses, and payroll. Changing these controls can test lower chair utilization, fee pressure, higher laboratory costs, or different salary budgets through linked calculations.
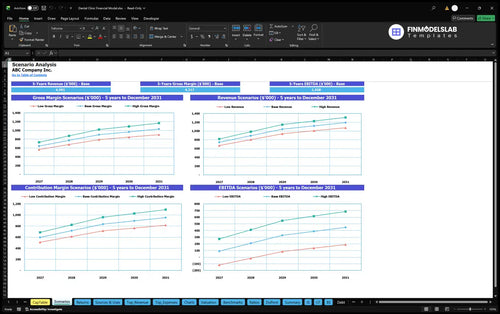
The Financial Scenario Analysis compares Low, Base, and High projections for revenue, gross margin, contribution margin, and EBITDA. Side-by-side results help show which dental clinic assumptions most affect operating outcomes before a financing or hiring decision.
These answers clarify what the workbook covers, what can be changed, and what the illustrative forecast does not establish.
Yes. Update chair capacity, clinical days, scheduled hours, and utilization in the Revenue inputs to recalculate the occupied-hour pool and projected sales.
No. The five services share one occupied chair-hour pool; the illustrated mix allocates half the hours to dentist services and half to hygiene.
Yes. The illustrated case allocates a $180,000 annual base to the owner dentist within the total $382,000 payroll forecast.
No. Startup capital purchases and other opening cash requirements are handled separately from the recurring expenses used to calculate EBITDA.
Yes. Dashboard debt controls feed financing schedules, while Cash Flow and Balance Sheet reports support analysis of repayments, working capital, and projected liquidity.
No. That is illustrative 2030 EBITDA, before depreciation, interest, income taxes, and other below-EBITDA items.
No. Returns, valuation, and scenario analyses depend on chosen assumptions; the supplied case does not establish a specific payback date or valuation.
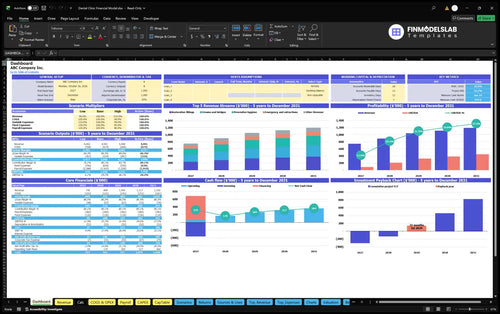
KPIs, forecasts, and cash flow at a glance.
Key assumptions and calculations driving revenue forecasts.
Funding sources, spending, and closing cash.
Cash break-even, payback, and ROIC.
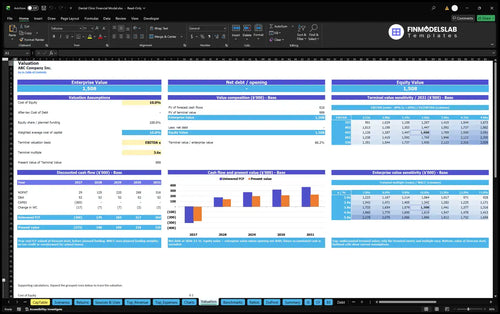
DCF valuation and sensitivity analysis.
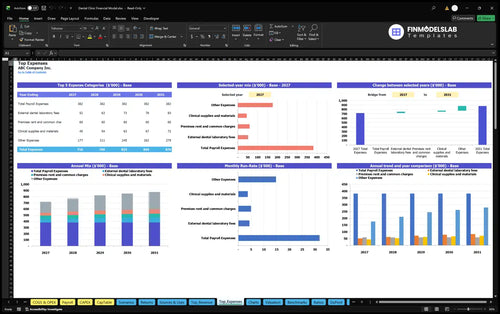
Largest costs and spending trends.
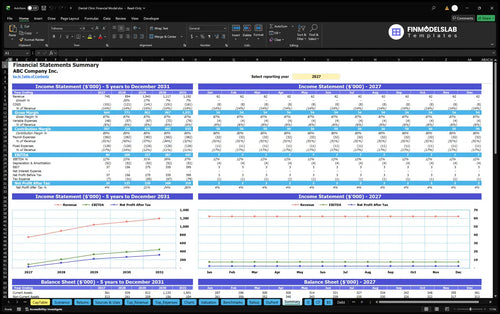
Annual and monthly financial performance.
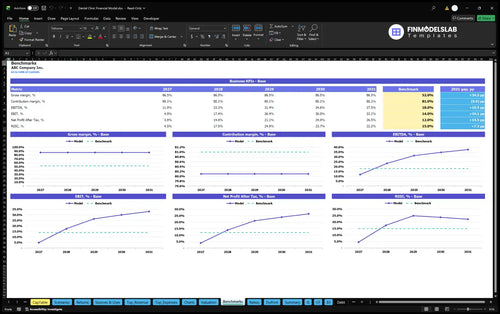
Compare margins and returns to benchmarks.

This template pulled pricing, staffing, and growth assumptions into one place, so I stopped chasing scattered inputs. I had a cleaner forecast in under an hour and could explain it without rebuilding the sheet.
I no longer had to worry that one bad cell would throw off the whole model. The structure made it easier to check my numbers, and I booked a planning call with my partner the same day.

The cash flow view made it much easier to spot shortfalls before they became a problem. I mapped out the next 12 months in one sitting and finally knew when we would need extra funding.