How Much Owner Income Can a Home Health Care Agency Generate?
For a U.S. owner-operated Home Health Care Agency focused on private-pay, non-medical personal care rather than Medicare-certified skilled home health, a stabilized base case can produce about $136,080 a year of owner income after a modeled 22% tax reserve and 8% reinvestment reserve on about $1.14 million of annual revenue. A conservative case falls to about $41,580, while a stronger scaled case reaches about $241,560. The base case assumes $95,000 of monthly revenue, roughly 2,714 billable care hours at a $35 blended hourly rate, $63,000 of monthly caregiver and office payroll, $7,000 of fixed overhead, $3,000 of marketing, $2,000 of debt service, and a 96% pre-labor gross margin because payroll is modeled separately. The estimate excludes Medicare skilled-home-health reimbursement economics, extraordinary legal or insurance claims, personal taxes beyond the modeled reserve, and any guaranteed owner distribution.
Owner income$136KNet margin12%Revenue for target pay$1.12MBusiness difficultyHard
How much can a Home Health Care Agency owner make?
The practical range in this model is about $42,000 to $242,000 a year after modeled reserves, with $136,080 as the base case. This article deliberately models a private-pay non-medical home-care agency: families buy caregiver hours for personal care, companionship, and help with daily activities. That matters because Medicare's home health coverage rules are built around intermittent skilled services and do not generally pay for custodial personal care when that is the only service needed. The customer-price anchor is the 2025 U.S. median of $35 per hour for a non-medical caregiver in the CareScout Cost of Care survey.
Revenue is not owner income. At $95,000 of monthly revenue, the model pays non-labor direct costs, caregiver and office payroll, overhead, marketing, and debt service. That leaves $16,200 of monthly profit before reserves; after $4,860 of modeled reserves, $11,340 remains as owner income. The owner may later split cash between salary and distributions, but the calculator does not double-count owner pay inside labor.
Owner income calculator
Estimate owner take-home from billings, labor, overhead, debt, reserves, and a target monthly pay level.
!
Planning note: Research-based planning estimate only. It is not guaranteed salary, tax advice, or owner distribution advice.
1
Billable care hours
2,714/mo
The base revenue target depends on keeping roughly 626 caregiver hours billed each week without letting uncovered shifts erase volume.
2
Hourly rate
$35/hr
The 2025 national median private-pay caregiver rate anchors the base case; local price and shift premiums can move owner cash quickly.
3
Loaded labor spread
$23.21/hr
Base payroll divided by billable hours shows the modeled caregiver-plus-office labor burden that must stay below the collected hourly rate.
4
Caregiver retention
75% turnover
Industry turnover makes recruiting and schedule coverage an income issue, not just an HR issue, because lost shifts reduce billable revenue.
5
Referral conversion
$3K/mo
The base marketing budget has to create retained client hours, not just leads; a handful of steady 20-hour-per-week clients can change scale.
6
Overhead and reserves
$93K/mo
About $93,006 of monthly revenue supports the modeled $10,000 owner-pay target after operating costs, debt, and reserves.
Want to test the owner-income assumptions in a full forecast?
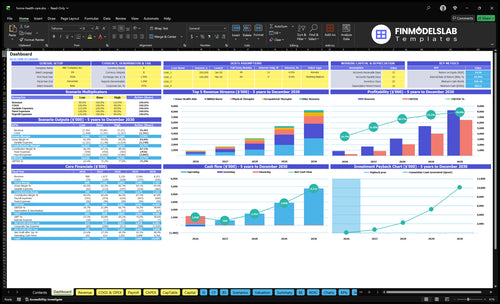
The Home Health Care Financial Model Template in Excel includes a business-specific dashboard. The preview helps an owner test service volume, staffing, cash balance, break-even, and low/base/high assumptions together instead of treating owner pay as a standalone percentage of revenue.
What revenue supports $120,000 of annual owner pay?
Under the base cost structure, about $93,006 per month, or roughly $1.12 million per year, supports a $10,000 monthly owner-pay target after the modeled 22% tax and 8% reinvestment reserves. Before any owner target or reserves, operating break-even is about $78,125 per month: $75,000 of operating costs divided by the 96% pre-labor gross margin. The broader 2022 Economic Census for Home Health Care Services shows how labor-heavy the category is, reporting $55.5 billion of payroll against $114.2 billion of revenue; that broad NAICS figure includes skilled and personal-care providers, so it is an adjacent scale benchmark rather than the margin assumption used here.
Base revenue math
$95,000 monthly billings equal $1.14 million annually.
At $35 per billed hour, that is about 2,714 hours per month.
Operating break-even before owner pay is about $78,125 monthly.
The $120,000 annual owner target needs about $93,006 monthly revenue.
What this estimate hides
Billable hours must actually be staffed and collected.
Weekend, overnight, and short-shift pricing may differ from the $35 anchor.
Client cancellations can cut revenue without reducing all office payroll.
State licensing and payer rules can add cost before the owner sees cash.
How do caregiver wages and staffing change owner distributions?
Labor is the largest controllable expense in this model. The BLS reported a $34,900 median annual wage for home health and personal care aides in May 2024, while employment is projected to grow 17% from 2024 to 2034. The base model spends $63,000 per month on caregiver wages, payroll burden, and office scheduling/recruiting payroll, or 66.3% of revenue. That is intentionally higher than a simple wage-to-revenue ratio because it includes payroll burden and the non-owner staff needed to keep shifts covered.
Retention also affects sales capacity. HCAOA's summary of the 2025 Activated Insights benchmarking report says professional caregiver turnover fell to 75.0% in 2024, still a very high replacement rate, while median customer growth was 2.9%. The same home-care benchmarking summary supports treating recruiting, training, and schedule continuity as margin drivers. A lower wage bill is not automatically better if it produces uncovered shifts, overtime, poor retention, and lost clients.
Base staffing discipline
Track labor dollars per billed hour, not payroll alone.
Separate caregiver payroll from scheduler and recruiter payroll.
Measure unfilled hours, overtime hours, and call-off replacement time.
Do not count the owner's labor as free passive profit.
Distribution sensitivity
A $1 increase in labor cost per billed hour costs about $2,714 monthly at base volume.
After the 30% combined reserves, that is about $1,900 less owner cash per month.
Annual owner income can therefore move by roughly $22,800 from a $1 hourly labor swing.
Pricing and scheduling must move with wage pressure.
Key Takeaways
The modeled base owner income is $136,080 after reserves on $1.14 million of annual revenue.
The agency needs roughly 2,714 billable hours per month at a $35 blended rate to support the base case.
Caregiver payroll, coverage, and retention matter more than headline gross margin because labor is modeled separately.
Safe distributions come only after debt, taxes, reinvestment, and working-capital needs are funded.
Can the agency run without the owner?
Yes, but the owner cannot assume the same distribution once a full management layer is hired. This base case is owner-operated: the owner leads sales, referral development, hiring decisions, escalation, and agency administration, while owner pay is the residual output rather than a payroll cost. A broader healthcare-management proxy from the BLS shows a $117,960 median annual wage for medical and health services managers in May 2024. A small non-medical agency may use a lower-paid administrator, but the benchmark shows why replacing the owner's management work can materially reduce distributions.
Here's the quick math: adding $8,000 a month of management payroll to the base case, with all else unchanged, reduces profit before reserves from $16,200 to $8,200. After the same reserves, modeled owner income falls to about $68,880 annually. The distinction between salary and distribution also matters for entity taxes. The IRS says S corporations must pay reasonable compensation to shareholder-employees for services before non-wage distributions are made. The calculator therefore shows economic owner cash, not a recommended payroll-versus-distribution split.
Owner-operated base
Owner handles leadership and referral development.
No owner salary is buried in the $63,000 labor line.
$136,080 is active-owner economic income after modeled reserves.
It should not be described as passive investment income.
Manager-run transition
Budget a real management salary and payroll burden.
Raise revenue or margin before expecting the old owner draw.
Document owner duties separately from capital distributions.
Re-test break-even after every management hire.
What do low, base, and high owner-income scenarios look like?
The low case produces $41,580 of annual owner income after reserves, the base case $136,080, and the high case $241,560. Costs rise with scale: labor moves from $46,000 to $99,000 per month, fixed overhead from $6,500 to $9,000, marketing from $2,500 to $4,500, and debt service from $1,800 to $2,500. Caregiver-retention pressure documented in the 2025 Activated Insights report is one reason the high case adds labor instead of holding costs flat.
Owner income scenarios
Low, base, and high cases connect billable hours, pricing, staffing, overhead, debt, and reserves to owner cash.
Home Health Care Agency low, base, and high owner-income planning cases.
Scenario
Low CaseLow income
Base CaseBase income
High CaseHigh income
Launch modelOperating posture
Slow client ramp with owner covering leadership and tight office staffing.
Stabilized owner-operated agency with steady private-pay referrals and schedule coverage.
Scaled local agency with stronger referral flow, more caregivers, and higher administrative capacity.
Typical setupRevenue and volume
$65,000 monthly revenue; about 1,900 monthly hours near a $34 blended rate; 95% pre-labor gross margin.
$95,000 monthly revenue; about 2,714 monthly hours at a $35 blended rate; 96% pre-labor gross margin.
$150,000 monthly revenue; about 4,050 monthly hours near a $37 blended rate; 97% pre-labor gross margin.
Cost driversMonthly cash load
Labor $46,000
Fixed overhead $6,500
Marketing $2,500
Debt $1,800
Reserves 30%
Labor $63,000
Fixed overhead $7,000
Marketing $3,000
Debt $2,000
Reserves 30%
Labor $99,000
Fixed overhead $9,000
Marketing $4,500
Debt $2,500
Reserves 34%
Owner income rangeAfter modeled reserves
$41,580
Annual owner income after modeled reserves.
$136,080
Annual owner income after modeled reserves.
$241,560
Annual owner income after modeled reserves.
Best fitHow to use it
Stress-test a slow launch, client losses, wage pressure, or periods when office costs cannot shrink with sales.
Use as the normal planning case for a stabilized owner-operated private-pay agency with disciplined staffing.
Test stronger local density and pricing while adding enough payroll, recruiting, and overhead to support the volume.
!
Planning note: These scenario figures are researched planning assumptions, not guaranteed earnings, salary promises, tax advice, or distribution forecasts.
What must be paid before owner cash is safe to distribute?
Safe owner cash starts after caregiver payroll, payroll taxes and benefits, office payroll, insurance, software, licensing and professional costs, marketing, debt service, taxes, and a working-capital reserve are funded. Debt deserves its own line because principal is a cash outflow even when it is not an income-statement expense. The SBA 7(a) program allows negotiated fixed or variable rates subject to program maximums, so a real loan payment can differ materially from the $2,000 monthly planning assumption used here.
For this base case, a six-week operating cushion is about $112,500, using the $75,000 monthly operating-cost base as a planning yardstick. That is not a statutory reserve requirement; it is a reasoned cash target to keep payroll moving through client churn, delayed long-term-care-insurance reimbursement, recruiting spikes, or insurance deductibles. If the agency expands into Medicare-certified skilled home health, the compliance and reimbursement model changes substantially: CMS certification requirements for home health agencies include skilled nursing, clinical records, professional oversight, and federal health-and-safety standards.
Cash waterfall
Collect client revenue.
Pay non-labor direct costs and all employee payroll.
Pay fixed overhead, marketing, and debt service.
Reserve for taxes, working capital, and reinvestment before drawing cash.
Do not mix these numbers
Revenue is client billings, not profit.
Operating profit is before owner reserves in this model.
Owner salary pays for work; distributions come from residual economics.
Cash safe to distribute is lower than accounting profit when debt and reserves consume cash.
Six detailed income drivers for a Home Health Care Agency
The six drivers below use the calculator assumptions. The $35 hourly caregiver price is a national starting point, not a universal local rate. Test every improvement through the same chain: billable hours and price create revenue; direct non-labor costs create gross profit; labor and overhead create operating profit; debt and reserves determine owner cash.
1. Billable care hours and schedule utilization
Fill hours before adding office cost
The base case needs about 2,714 billed hours per month, or roughly 626 hours per week, to support $95,000 of monthly revenue at the $35 blended rate. That is a capacity target, not merely a sales target: every sold shift must have an available caregiver, an acceptable travel radius, and a client who actually receives and pays for the service. At base economics, an extra 100 billable hours creates $3,500 of revenue and about $3,360 of pre-labor gross profit. If incremental loaded labor runs near the modeled $23.21 per billed hour, those hours add about $1,039 of profit before reserves and roughly $727 of owner cash after the 30% combined reserve, before any new fixed cost.
Track hours by week, client, caregiver, and daypart. Cancellations and call-offs can create office work without billings, so the practical revenue ceiling is the lesser of demand and reliably staffed hours.
Track the fill rate weekly
Use schedule utilization as the bridge between sales and cash.
Billable hours sold versus delivered
Unfilled and cancelled hours
Overtime hours used to rescue shifts
Revenue per active caregiver
2. Hourly rate and service mix
Price small changes across thousands of hours
The 2025 national median of $35 per hour is a useful starting anchor, but local rates differ by state, metro area, care intensity, minimum shift length, weekends, and nights. A $1 increase across the base 2,714 monthly hours adds $2,714 of monthly revenue. With a 96% pre-labor gross margin and no immediate change in staffing cost, that creates about $2,605 of extra profit before reserves and roughly $1,824 of additional owner cash after the 30% reserve. The reverse is also true: discounting by $1 across the whole book can remove more than $21,000 of annual owner cash if hours do not increase enough to compensate.
Long recurring shifts can be easier to staff than scattered short visits. Weekend or higher-acuity premiums help only when the related caregiver wage and training costs are modeled too.
Manage realized rate, not list price
The useful KPI is collected revenue divided by delivered hours.
Blended collected rate per hour
Discounts and waived minimums
Weekend and overnight premiums
Rate increase retention by client cohort
3. Loaded caregiver and office labor cost
Protect the spread between billing and labor
Base labor cost is $63,000 per month, or $23.21 per billed hour at 2,714 hours. That includes caregiver wages, payroll burden, and office scheduling/recruiting payroll. As an adjacent compensation check, the BLS March 2026 service-occupation data reports $18.15 per hour in wages plus $5.48 in employer benefit costs across private-industry service jobs. Home care will not match that aggregate exactly, but it shows why budgeting only the posted caregiver wage understates employer cost.
At base volume, every $1 increase in labor cost per billed hour removes about $2,714 of monthly profit before reserves and roughly $1,900 of monthly owner income after reserves, or about $22,800 a year. The response may be higher pricing, denser schedules, better retention, or less overtime; cutting caregiver pay can also reduce capacity.
Watch labor dollars per delivered hour
Separate each source of labor pressure so the fix is specific.
Caregiver wage per hour
Payroll taxes and benefits
Overtime and shift differentials
Scheduler and recruiter payroll per billed hour
4. Caregiver retention and local route density
Reduce uncovered hours before chasing more leads
High turnover creates a double cost: recruiting expense rises while sold hours go unfilled. HCAOA's 2026 summary of a caregiver recruitment study found that 76% of hires lived within 20 miles and that faster interview response improved hiring. That supports a local-density strategy: recruit close to client clusters, shorten caregiver travel, and respond to applicants quickly.
If 5% of base hours go unfilled, about 136 hours and $4,760 of monthly revenue disappear. After avoided caregiver labor, the missed contribution is roughly $1,400 before reserves and about $1,000 of owner cash per month. Repeated coverage failures can also cost the recurring client relationship.
Measure retention as a revenue KPI
Staff stability is valuable when it keeps recurring client hours billable.
90-day caregiver retention
Applicant-to-hire conversion
Average caregiver commute radius
Unfilled hours caused by staffing
5. Referral conversion and client retention
Buy recurring hours, not raw leads
The base model allocates $3,000 per month to marketing and referral development. That number is a planning assumption, so the return must be measured internally. One client using 20 hours a week at $35 per hour produces about $700 of weekly billings and roughly $3,033 in an average month. Five retained clients at that utilization add about $15,167 of monthly revenue. If $3,000 of marketing produced those five retained starts, the simple media-and-outreach spend would be about $600 per retained client before counting sales labor, assessment time, and caregiver recruiting.
Retention matters more than the first invoice. Separate professional referrals, community outreach, paid search, insurance inquiries, and family referrals so each channel is judged on retained billable hours rather than inquiry volume.
Track acquisition through 90 days
Connect each source to hours that are still billing after onboarding.
Cost per retained client start
Hours per new client at 30 and 90 days
Referral-source conversion rate
Client churn and lost weekly hours
6. Fixed overhead, debt service, and reserve discipline
Keep owner draws behind the cash floor
The base agency carries $7,000 of fixed overhead, $3,000 of marketing, and $2,000 of debt service each month in addition to $63,000 of labor. That creates $75,000 of monthly operating costs and a pre-owner break-even revenue of about $78,125 at a 96% gross margin. Every extra $1,000 of fixed monthly cost therefore needs about $1,042 of additional revenue just to keep profit before reserves unchanged. Debt has the same cash effect: another $1,000 of monthly principal and interest raises the operating revenue need even though principal is not an accounting expense.
Reserves decide whether accounting profit becomes safe owner cash. The base case holds 22% for taxes and 8% for reinvestment, leaving $11,340 from $16,200 of monthly profit before reserves. A separate six-week cushion of roughly $112,500 is a planning target, not part of the calculator formula. Below that floor, distributions should normally shrink before required payments do.
Run a weekly cash-waterfall check
Owner income is the last claim on cash, not the first.
Four- to six-week payroll and overhead runway
Debt-service coverage
Tax reserve balance
Reinvestment and insurance-deductible reserve
Disclaimer
Financial Models Lab provides this article and its calculators for educational and business-planning purposes only. They are not personalized financial, accounting, tax, legal, investment, or lending advice. Figures shown are illustrative planning estimates based on publicly available sources, observed market information, and stated assumptions; they are not guaranteed benchmarks, forecasts, quotes, or expected results. Actual startup costs, revenue, expenses, margins, funding needs, and break-even timing vary by location, date, business size, operating model, financing, and execution. Review the cited sources and replace sample assumptions with current local data, supplier quotes, and your own operating inputs. Calculator and financial-model outputs change when assumptions change. Consult qualified professional advisers before making material commitments. Financial Models Lab sells related templates and may link to its own products. Please report suspected errors through our contact page.
Home Health Care Agency Bundle
Choosing a selection results in a full page refresh.