

Revenue and Calc
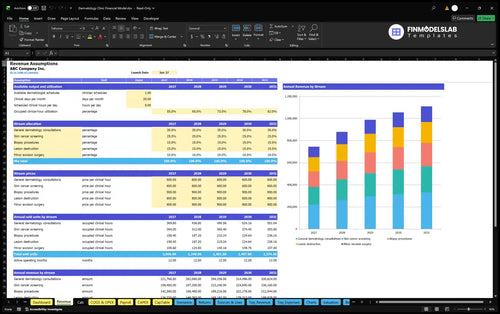
Enter physician schedules, working days, daily hours, utilization, and allocation by service. Monthly calculations apply capacity and realized hourly fees, then consolidate revenue across five mutually exclusive activities.


The Dermatology Clinic Financial Model is an Excel planning template for an independent outpatient practice. It connects one dermatologist’s scheduled clinical hours, procedure mix, realized professional fees, staffing, operating expenses, and opening investment to monthly calculations and financial reports.
The illustrated case is a leased, 2,400-square-foot clinic in suburban Columbus, Ohio, with three exam/procedure rooms and a 2026–2030 forecast. It covers medical dermatology, screenings, biopsies, lesion destruction, and minor excisions, not Mohs surgery, cosmetic services, retail, or hospital fees.
The workbook links editable operating assumptions to clinical revenue calculations, personnel and expense schedules, funding plans, and decision-oriented reports.
Enter physician schedules, working days, daily hours, utilization, and allocation by service. Monthly calculations apply capacity and realized hourly fees, then consolidate revenue across five mutually exclusive activities.
Plan clinical consumables, purchased technical services, collection fees, processing, marketing, premises expenses, and base salaries. Payroll also supports role-level staffing dates, annual FTE plans, and compensation controls.
Record opening medical equipment and fit-out, equity contributions, and optional financing facilities. CAPEX schedules purchases and depreciation; the Debt worksheet follows borrowing, interest, principal repayments, and balances.
Review the Income Statement, Cash Flow Statement, Balance Sheet, Summary, Scenarios, Returns, financial Charts, Benchmarks, and related ratio and valuation tools. Model Checks help identify inconsistencies.
Revenue is calculated from one dermatologist’s occupied clinical hours, split once among five service categories and priced using net realized fees per hour.
The case uses one clinician schedule, 20 clinical days per month, and eight scheduled hours per day. Occupied-hour utilization rises from 55% in 2026 to 82% in 2030; three exam rooms enable workflow but do not create additional physician capacity.
Clinical time is allocated 35% to general consultations, 25% to skin cancer screening, 15% to biopsy, 15% to lesion destruction, and 10% to minor excision. Realized hourly yields are $600, $600, $900, $800, and $900, respectively.
The Revenue Forecast translates clinical days, scheduled hours, utilization, service-hour allocations, and hourly yields into monthly activity and annual professional fees. Each occupied hour is assigned to only one service, so categories do not duplicate capacity.
1 physician × 20 days/month × 8 hours/day × 55% utilization × $705 weighted hourly yield × 12 months = $744,480.
The $705 weighted yield follows the five service shares and their respective fees. The modeled revenue is net of contractual discounts; external laboratories and pharmacies bill patients separately, and no demand cap or cosmetic-service revenue is included.
The clinic separates revenue-linked direct costs, variable operating expenses, recurring fixed overhead, and role-based payroll without counting salaries twice.
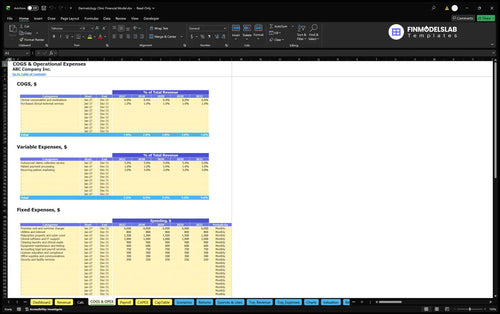
Clinical consumables and medications equal 6% of revenue, while purchased technical services add 1% in COGS. Collection outsourcing is 5%, payment processing 1%, and recurring marketing 3% in variable operating expenses.
Fixed overhead covers rent, utilities, insurance, software, cleaning and waste, maintenance, professional services, licenses, supplies, and facility security. Included premises rent and common charges are estimated at $6,000 monthly, within the total $151,200 annual fixed-cost plan.
The COGS and Operating Expenses forecast organizes direct clinical costs, revenue-linked servicing costs, and monthly overhead. Changing a spending rate or expense timing shows how expense totals and operating margins respond as clinical revenue increases.
| Category | Planning basis | 2026 | 2030 |
|---|---|---|---|
| COGS | 7% of revenue | $52,114 | $77,697 |
| Variable expenses | 9% of revenue | $67,003 | $99,896 |
| Fixed overhead | Monthly fixed amounts | $151,200 | $151,200 |
| Payroll | Fixed base compensation | $539,000 | $539,000 |
Amounts are rounded independently; expense categories exclude startup investing and owner contributions.
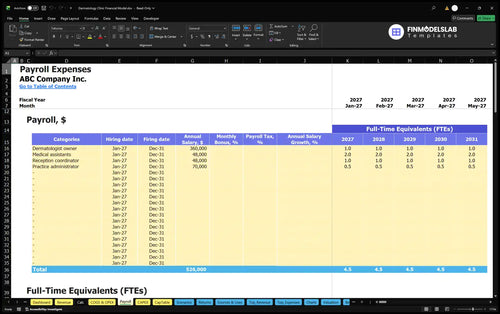
The staffing plan contains a dermatologist owner at $360,000 annually, two medical assistants at $48,000 each, a receptionist at $48,000, and a half-time administrator at a $70,000 annual full-time rate. That equals 4.5 annual-average FTE and $539,000 of annual base payroll.
The Payroll Forecast displays role-level staffing, full-time-equivalent plans, salary assumptions, and monthly personnel expense calculations. In this case the owner-physician’s full fixed base compensation is charged before EBITDA, rather than treated as an unrecorded owner draw.
Opening investment is tracked separately from annual operating expenses, allowing equipment, preopening items, working capital, and reserves to be evaluated on their own terms.
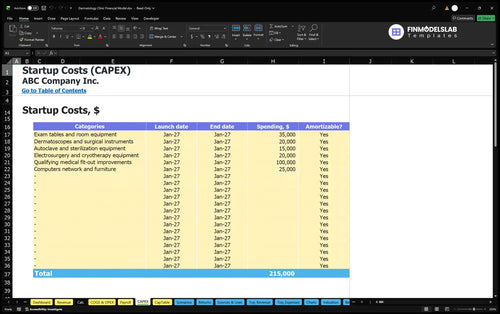
The illustrative opening budget includes $215,000 of startup assets: clinical room equipment, instruments, sterilization equipment, cryotherapy/electrosurgery equipment, medical fit-out, and technology or furniture. Separate non-asset startup cash of $62,000 covers deposits, credentialing, permits, website work, preopening services, and training.
The funding plan also includes $42,833 of opening net working capital and a $202,329 three-month reserve. Accounts receivable days are 21, accounts payable days 26, and inventory days 26; these are model inputs, not proof of actual cash sufficiency.
The Capital Expenditure Plan schedules equipment purchases and qualifying fit-out, identifies depreciable items, and tracks resulting depreciation and asset balances. It distinguishes capital investment from consumables, salaries, and recurring clinic overhead.
$215,000 startup assets + $62,000 other opening cash + $42,833 opening working capital + $202,329 reserve ≈ $522,162 initial owner funding.
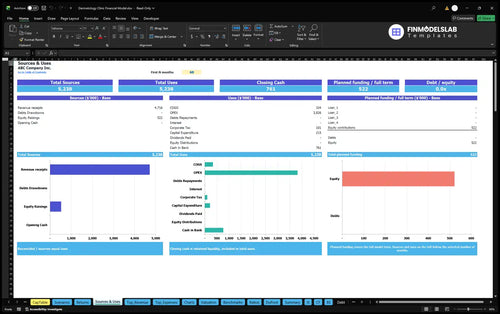
The Sources and Uses of Funds report reconciles cash inflows and outflows for a selected period, including equity, debt, operating activity, and investments. The sample opening plan is owner-funded; no committed outside borrowing is assumed.
The model case shows annual revenue and operating costs through EBITDA as utilization increases while planned base payroll and fixed overhead remain constant.
| Year | Revenue | Operating Expenses | EBITDA |
|---|---|---|---|
| 2026 | $744,480 | $809,317 | -$64,837 |
| 2027 | $879,840 | $830,974 | $48,866 |
| 2028 | $988,128 | $848,300 | $139,828 |
| 2029 | $1,055,808 | $859,129 | $196,679 |
| 2030 | $1,109,952 | $867,792 | $242,160 |
Case projections, not historical performance or industry benchmarks. Rounded amounts may differ slightly from underlying formulas.
The example moves from negative $64,837 EBITDA in 2026 to positive $48,866 in 2027, reaching $242,160 in 2030. The change reflects higher utilization of one physician’s hours, not additional physician schedules or a larger clinical room count.
The Income Statement can show depreciation, financing costs, taxes, and accounting profit, but none of those case results are specified here. EBITDA alone does not establish net profit, free cash flow, or the month an opening investment is recovered.
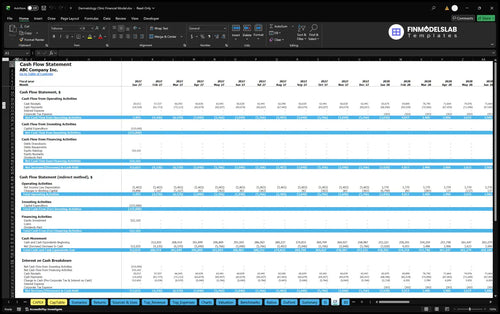
The Cash Flow Forecast separates operating, investing, and financing cash movements and reconciles opening to closing cash. It supports analysis of patient collection timing, equipment purchases, owner equity, and any financing assumptions entered into the workbook.
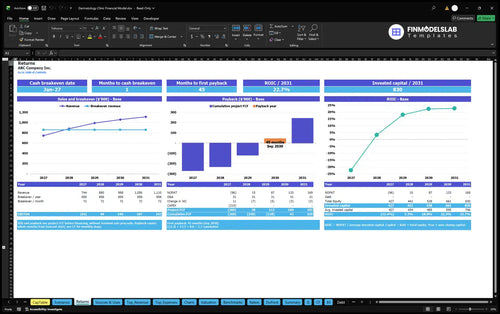
Dedicated Returns and scenario tools help compare the clinic’s operating thresholds, cash recovery, and financial sensitivity without equating these measures with EBITDA.
Sales break-even estimates the revenue needed to cover defined operating costs, while cash break-even considers cash timing. Investment payback measures recovery of committed capital through project cash flow; annual return on invested capital compares operating returns with invested capital.
The published case brief does not provide a verified break-even sales level, payback month, annual ROIC, or valuation. Those outputs depend on the workbook’s linked assumptions and should not be inferred from the EBITDA table.
The Returns report compares sales break-even, cash break-even, investment payback, and annual ROIC as distinct measures. It helps evaluate whether the clinic can cover operating requirements and whether projected project cash flows recover its investment.
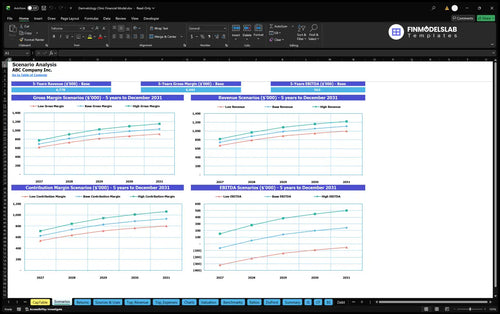
Dashboard scenario controls provide Low, Base, and High multipliers for revenue, COGS, variable expenses, fixed expenses, and payroll. These allow the same one-physician practice to be assessed under different fee realization, utilization-related revenue, and cost conditions.
The Financial Scenario Analysis compares Low, Base, and High cases for revenue, gross margin, contribution margin, and EBITDA. It helps test how modeled clinic economics change when the user selects alternative operating and expense multipliers.
The template is suited to evaluating a single-provider outpatient medical dermatology practice and customizing its assumptions before drawing investment conclusions.
Use the Revenue and Payroll worksheets to test appointments-equivalent clinical hours, service mix, staffing costs, and margin sensitivity. Check the Dashboard and financial statements before using projections in a business plan.
A multi-provider clinic, Mohs lab, aesthetics platform, or retail-heavy practice requires different operating assumptions and possibly a customized model. The illustrated Ohio case is a planning example, not a representation of local medical reimbursement or financial performance.
Answers to common questions about the forecast logic, editable assumptions, included reports, and limits of the illustrated case.
Yes. The Revenue worksheet includes editable physician capacity, utilization, service-hour allocations, and hourly realized fees that drive the monthly revenue forecast.
No. The example has one dermatologist-hour capacity pool. Its three rooms support the schedule rather than multiply one physician into three independent providers.
No. The documented case includes general dermatology, screenings, biopsies, lesion destruction, and minor excision, without Mohs laboratories, lasers, injectables, or retail.
Yes. The sample charges the owner dermatologist’s $360,000 annual base salary through Payroll before calculating EBITDA.
The workbook includes projected Income Statement, Cash Flow Statement, and Balance Sheet reports, plus a combined Summary and supporting operating, financing, and scenario schedules.
No. EBITDA excludes investing and financing cash movements. Review Cash Flow, working capital assumptions, startup outlays, and the Balance Sheet to assess liquidity.
No. The source provides annual operating results through EBITDA, not verified case net profit, payback timing, ROIC, or a tested cash-adequacy conclusion.
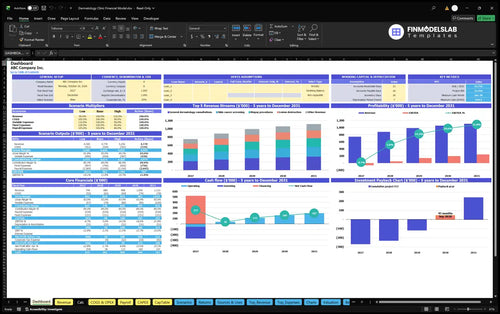
KPIs, forecasts, and cash flow at a glance.
Key assumptions and calculations driving revenue forecasts.
Funding sources, spending, and closing cash.
Cash break-even, payback, and ROIC.
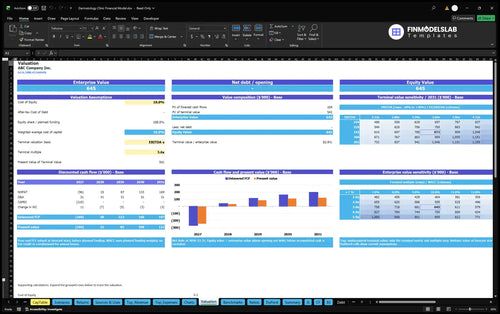
DCF valuation and sensitivity analysis.
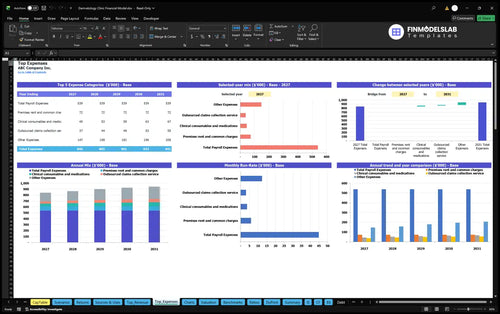
Largest costs and spending trends.
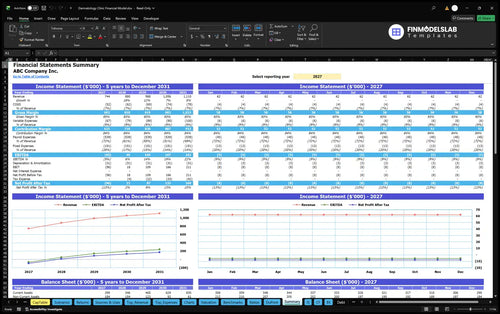
Annual and monthly financial performance.
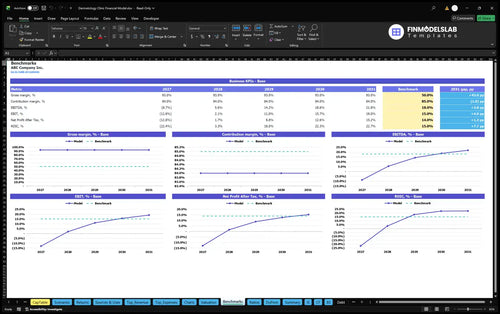
Compare margins and returns to benchmarks.

Building the dermatology model by hand would’ve eaten up my week. This template cut the setup to a few hours, and I could move straight into planning instead of wrestling with spreadsheets.
I used to keep statements and charts in separate files, which made every update a mess. Now everything sits in one place, and I had a clean set of reports ready for my meeting without chasing tabs.
The cash flow section made runway and shortfalls much easier to see. I could spot a funding gap early and book a follow-up call with confidence instead of guessing month by month.